Articoli

Tutto sul nostro settore


Modulation of the anticancer immunity by natural agents: inhibition of T regulatory lymphocyte generation by arabinoxylan in patients with locally limited or metastatic solid tumors

lissoniResearch Article (download PDF version)

Paolo Lissoni1,*, Giusy Messina1, Fernando Brivio2, Luca Fumagalli2, Luigi Vigoré3, Franco Rovelli3, Luisa Maruelli4, Mauro Miceli4, Paolo Marchiori4, Giorgio Porro1, Michael Held5, Giuseppe di Fede6, Toshi Uchiyamada7

1 Division of Radiation Oncology, San Gerardo Hospital, Milan, Italy
2 Division of Surgery, San Gerardo Hospital, Milan, Italy
3 Laboratory of Immunomicrobiology, San Gerardo Hospital, Milan, Italy
4 Natur-Spiritual, Milan, Italy
5 Biological Medicine Center, Rome, Italy
6 Institute of Biological Medicine, Milan, Italy
7 Daiwa Pharmaceuticals, Tokyo, Japan

dr. Paolo Lissoni

*Correspondence: Dr. Paolo Lissoni, Divisione di Radioterapia Oncologica, Ospedale S.Gerardo, 20052 Monza, Milano, Italy; Fax: +390392332284, e-mail: p.lissoni@hsgerardo.org
Key words: Anticancer immunity, arabinoxylan, immunostimulation, T regulatory lymphocytes
Abbreviations: interleukin 10, (IL-10); interleukin 6, (IL-6); interleukin-2, (IL-2); interleukn 12, (IL-12); NK cells, (CD16+CD56+); T cytotoxic lymphocytes, (CD8+); T helper lymphocytes, (TH), (CD4+); T lymphocites, (CD3+); Transforming growth factor beta, (TGF-β) T-regulatory lymphocytes, (T-reg), (CD4+CD25+)

Received: 30 September 2008; Revised: 1 November 2008
Accepted: 17 November 2008; electronically published: December 2008

Summary

In the last years, several immunomodulating antitumor agents have demonstrated in the nature, particularly from Aloe plant and rice bran. However, the major problem concerning the natural antitumor agents is to define their immune mechanisms of action in relation to the more recent advances in tumor immunobiology. At present, the main cause responsible for the lack of an effective antitumor response in advanced cancer patients is belived to be represented by the generation of a subtype of T helper lymphocytes (CD4+) with suppressive activity on anticancer immunity, the so-called T regulatory lymphocytes (T reg), which may be clinically identified as CD4+CD25+ cells. On this basis, a study was planned to evaluate the effect of rice bran extract arabinoxylan on T reg cell count and percentage in solid tumor patients in relation to the various lymphocyte subpopulations. The study included 22 evaluable cancer patients, 16 of whom had an untreatable metastatic solid tumor. Arabinoxylan was given orally at a dose of 2000 mg/day for the first month, followed by a dose of 1000 mg/day for the next month. In each patient we evaluated by monoclonal antibodies the absolute number of lymphocytes, T lymphocytes (CD3+), T helper (TH) lymphocytes (CD4+), T cytotoxic lymphocytes (CD8+), NK cells (CD16+CD56+), T reg lymphocytes (CD4+CD25+) and TH/T reg ratio before and after 2 months of therapy. No substantial change occurred on therapy in the mean number of lymphocytes, CD3+, CD8+ and NK cells. On the other hand, the mean number of TH cells increased, whereas that of T reg cell decreased on treatment, even though none of these differences was statistically significant. On the contrary, TH/T reg mean ratio significantly enhanced after arabinoxylan therapy. In addition to its previously demonstrated stimulatory action on NK function, this study shows that arabinoxylan may inhibit the production of T reg cells, which are responsible for cancer-related immunosuppression, with a following improvement in the anticancer immunity. If further studies will confirm these results, arabinoxylan could be successfully associated with chemotherapy to induce not only a cytotoxic destruction of cancer cells, but also an improvement in the immune status.

I. Introduction
The recent advances in the definition of the mechanisms responsible for tumor progression have suggested the possibility to control cancer growth not only trough chemotherapy-induced cancer cell destruction, but also by stimulating the anticancer immunity. In addiction to the exisence of endogenous antitumor molecules, several agents capable of stimulating the anticancer immunity have alsso isolated from plants. However, the immunomodulatory effects of most natural immunomodulating agents need to be better investigated in an attempt to establish their mechanisms of action in relation to the most recent discoveries concerning the physiopathology of the anticancer immunity. At present, Aloe extracts (Lissoni et al, 1998) and arabinoxylan extract from rice bran (Ghoneum and Jewett, 2000) would represent some of the potential natural agents which could be utilized in the complementary therapy of human neoplasms. Today, it is known that the antitumor immune response is the end-result of several interactions involving cytokines and immune cells, provided by stimulatory or suppressive effects on the anticancer immunity (Atzpodien and Kirchner, 1990; Rosenberg, 1992). Therefore, the lack of an effective anticancer immune response in most cancer patients with advanced disease would simply depend on the prevalence of immunosuppressive mechansisms with respect to the immunostimulatory ones (Atzpodien and Kirchner, 1990). The anticancer immunity is mainly activated by T helper-type 1 lymphocytes by releasing IL-2 (Whittington and Faulds, 1993), and by dentritic cells, which act as antigen-presenting cells producing IL-12 (Banks et al, 1995), T cytotoxic lymphocytes and NK-LAK system, which are involved in the induction of the antigen-dependent and antigen-independent cytotoxicity, respectively (Atzpodien and Kirchner, 1990). Therefore, IL-2 and IL-12 would represent the main anticancer cytokines in humans. On the contrary, the suppression of the anticancer immune response is mediated by several cytokines, namely IL-10 (Moore et al, 1993), IL-6 (Matsuda and Hirano, 1990) and TGF-β (Shevach, 2002). Recently, however, it has been demonstrated that the various endogenous suppressive factors would exert their inhibitory immune effect through a common end-mechanism, consisting of the generation of a subtype of T helper lymphocytes (CD4+cells), provided by a fundamental suppressive activity on the anticancer immunity, the so-called T regulatory lymphocyte (T reg) (Dieckmann et al, 2001), which at present seems to constitute the main mechanism responsible for cancer-related immunosuppressive status. T reg cells may be identified by the simultaneous expression of the alpha-chain of IL-2 receptor (CD25) and CD4 antigen (Dieckmann et al, 2001). Then, T reg cells may be clinically recognized as CD4+CD25+ lymphocytes. Therefore, each eventual natural immunomodulating agent would have to be investigated in relation to its possible effect on T reg generation since, at least from a theoretical point of view, each natural agent capable of counteracting T reg activity could positively influence the prognosis of the neoplastic disease by improving the efficacy of the anticancer immune response. Moreover, our previous preliminary studies have suggested that the percentage of T reg cells with respect to the total number of T helper cells, as expressed as CD4/CD4CD25 ratio, may represent an optimal synthetic immune index to investigate the functional status of the anticancer immunity in the single cancer patient, by representing the synthesis of the actions of the great number of immunostimulating and immunosuppressive factors involved in the modulation of the anticancer immunity (Dieckmann et al, 2001). Within the great number of natural agents derived from plants and potentially usefull to be employed in the complementary therapy of cancer, arabinoxylan would seem to represent one of the potential natural agent, because of its efficacy in improving the clinical status of cancer patients (Ghoneum and Jewett, 2000; Ghoneum and Gollapudi, 2005; Markus et al, 2006; Ghoneum et al, 2007). The immunomodulating properties of this nautral substances extracted from plants have been confirmed by experimental studies, but unfortunately most experiments have been limited to the investigations of they effects on non-specific immune parameters for the anticancer immunity, such as NK cell cytotoxicity. In contrast, since reg cells play a fundamental role in suppressing the generation of the anticancer immunty, each potential antitumor immunomodulatory natural substances, would have to be investigated also in relation to their eventual influence on T reg cell system. On the basis of the recent discoveries in tumor immunobiology (Dieckmann et al, 2001; Shevach, 2002), a study was planned to investigate the possible influence of arabinoxylan on both absolute number of T reg cells and their ratio with respect to the total CD4+ T cells in a group of solid tumor patients, affected by locally limited or metastatic disease.

II. Materials and methods
The study included 24 consecutive patients, 18 of whom had a metastatic solid tumor, which did not respond to the conventional anticancer chemotherapies and for whom no other effective standard treatment was available, while the remaining 6 patients had been surgically treated for a locally limited neoplasm. Patients were followed at Biological Medical Institute of Milan and the protocol was approved by the Director of the Institute. Eligibility criteria were, as follows:histologically proven locally limited or metastatic solid tumor, no double tumor, no chronic therapy with corticosteroids because of their immunosuppressive effects and no concomitant treatment with other immunomodulating agents,such as interferons,interleukins and monoclonal antibodies. At the time of the start of arabinoxylan therapy, patients with untreatable metastatic cancer were under treatment with the only supportive care, consisting of anti-inflammatory agents for pain, anti-dopaminergic drugs for nausea and vomiting and with the pineal hormone melatonin for the therapy of the neoplastic cachexia (Banks et al, 1995). Patients were considered as fully evaluable when they had received arabinoxylan therapy for at least 2 consecutive months. Arabinoxylan was given orally at a dose of 1000 mg twice/day for the first month, followed by a dose of 1000 mg/day for the next month. Arabinoxylan was supplied by DAIWA Pharmaceutical (Tokyo, Japan). It was derived from rice bran treated enzymatically with an extract of the shiitake mushrooms. It is a polysaccharide containing β-1,4-xylopironase hemicellulose, commercially available and known as Biobran. For the immune investigation, venous blood samples were collected in the morning after an overnight fast before the onset of arabinoxylan therapy and after 2 consecutive months of treatment. In each blood sample, we evaluated the absolute number of total lymphocytes, T lymphocytes (CD3+), T helper (TH) lymphocytes (CD4+), T cytotoxic lymphocytes (CD8+), NK cells (CD16+ CD56+ and T regulatory (T reg) lymphocytes (CD4+ CD25+). The different lymphocyte subsets were measured with a flow cytometric assay by using specific monoclonal antibodies supplied by Becton-Dickinson (Milan, Italy). Moreover, because of the importance not only of their absolute number, but also of their percentage with respect to the other lymphocyte subsets, namely to that of CD4+ cells, CD4/CD4CD25 ratio, corresponding to TH/T reg ratio, was also determined before and after therapy. Normal values (95% confidence limits) of T reg number and TH/T reg ratio observed in our laboratory were below 240/mm3 and above 4.0, respectively. Data were reported as mean +/- SE and statistically analyzed by the Student’s t test, the analysis of variance and the chi-square test, as appropriate.

III. Results
Evaluable patients were 22/24, while the remaining 2 patients, both affected by untreatable disseminated liver metastases due to colorectal cancer, rapidly died for disease progression before concluding the two planned months of arabinoxylan therapy. The clinical characteristics of the evaluable patients are reported in Table 1. Figure 1 illustrates changes in the mean number of total lymphocytes, T lymphocytes, T cytotoxic lymphocytes and NK cells occurring after 2 months of arabinoxylan therapy. No substantial variation was found in the mean number of lymphocytes, T lymphocytes, T cytotoxic lymphocytes and NK cells under arabinoxylan treatment. In contrast, as illustrated in Figure 2, TH and T reg mean numbers increased and decreased, respectively, after arabinoxylan therapy, without, however statistically significant differences with respect to the values seen prior to therapy. On the contrary, a statistically significant increase in TH/T reg mean ratio was achieved after arabinoxylan therapy (p<0.025). The increase in TH/T reg ratio under arabinoxylan therapy was more pronounced in patients with an abnormally low ratio prior to therapy with respect to that occurring in those with normal pre-treatment ratio, however without statistically significant differences ( 2.3 +/- 0.4 vs 1.7 +/- 0.5). In more detail,

090722_linfocitiT_table1
090722_linfocitiT_1

Figure 1. Changes in the number of lymphocytes, Tlymphocytes (CD3), T cytotoxic lymphocytes (CD8) and NK cells (CD16 CD56) after 2 months of arabinoxylan therapy.
090722_linfocitiT_2

Figure 2. Changes in the mean number of T helper (TH) lymphocytes (CD4) and T regulatory lymphocytes (cd4 cd24) and in TH/T reg mean ratio.

before arabinoxylan therapy, an abnormally low TH/T reg ratio was present in 12/22 (55%) evaluable patients. Arabinoxylan treatment induced a normalization of TH/T reg ratio in 5/12 (42%) patients with an abnormally low ratio prior to therapy. The percentage of arabinoxylan-induced TH/T reg normalization obtained in lymphocytopenic patients was not significantly different from that achieved in patients with normal pre-treatment lymphocyte count ( 3/7(43%) vs 2/5(40%) ). No toxicity was observed under arabinoxylan treatment, which was well tolerated in all patients. Asthenia was present in 8/22 (36%) evaluable patients. An evident relief of asthenia, as assessed by a specific patient report, was obtained under arabinoxylan therapy in 5/8 (63%) patients.

IV. Discussion
Previous experimental studies had already demonstrated some immunomodulating properties of arabinoxylan, in particular consisting of stimulation of NK cytotoxic function (Ghoneum, 1998), whereas NK cell number did not seem to be influenced by arabinoxylan administration. However, it has to be remarked that NK cells were belived to be fundamental in the antitumor immunity until some years ago, before the discovery of the essential role played by the antitumor cytokines, such as IL-2 and IL-12 (Whittington and Faulds, 1993) and dendritic cells, because of their function as antigen-presenting cells (Banks et al, 1995). In fact, it has to be considered that the cytotoxic activity of NK cells is effective only against artificial laboratory cancer cell lines, whose biological malignant properties are different from those presented by fresh human tumor cells (Whittington and Faulds, 1993). In addition, NK cells have been proven to be also able to destroy fresh human cancer cells only after the activation of their cytotoxic function by IL-2 (Atzpodien and Kirchner, 1990). From this point of view, arabinoxylan had been already proven to amplify the stimulatory effect of IL-2 on NK-mediated antitumor cytotoxicity (Ghoneum and Jewett, 2000). In contrast, no study has been performed up to now to evaluate the possible influence of arabinoxylan not only on the mechanisms responsible for the generation of an effective anticancer immune response, but also on those involved in the suppression of anticancer immunity. The results of this preliminary study, carried out to evaluate the influence of arabinoxylan on T reg cells, which represent the most important cells involved in the suppression of the antitumor cytotoxic immune response, demonstrates that arabinoxylan may counteract T reg cell generation by reducing their number and percentage with respect to the total amounts of CD4+ cells and circulating lymphocytes. Since NK cell function is inhibited by T reg activation (Shevach, 2002), the previously demonstrated arabinoxylan-induced stimulation of NK cell cytotoxic function might depend at least in part on its capacity of counteracting T reg generation (Dieckmann et al, 2001). Moreover, this study would suggest that the inhibitory action of arabinoxylan on T reg generation is more pronounced in patients with an abnormally high percentage of T reg cells prior to therapy, with a following pre-treatment abnormally low TH/T reg ratio before therapy, whereas its effect was less evident in patients with a pre-treatment value of TH/T reg ratio within the normal range. Therefore, the influence of arabinoxylan on T reg generation would consist of a modulatory action rather than an inhibitory activity. This finding could explain a potential favourable immunomodulatory effect of arabinoxylan also in patients with autoimmune diseases (Ghoneum, 1998), who in contrast to cancer patients would tend to present abnormally low amounts of T reg cells. In any case, the importance of the inhibition of T reg generation in the induction of an effective anticancer immune response has been recently confirmed by the evidence that the block of T reg activity by specific monoclonal antibodies may induce objective tumor regressions in humans (Yang et al, 2007). Obviously, the major problem is the exact identification of he T reg cell population. Even though T reg cells may express other immune markers, namely FOX-p2 cytoplasmatic antigen, most clinicians are in agreement to identify the CD4+CD25+ cells as T reg lymphocytes (12). In any case, further studies, by evaluating other immune markers, will be required to better identify T reg cells population, namely FOX-p3, even though recently some Authors have shown that FOX-p3 expression by T reg cells is associated with a lower suppressive activity (Dieckmann et al, 2001; Shevach, 2002). Moreover, it has to be remarked that several patients included in the present study were concomitantly under palliative therapy with the anti-cachectic pineal hormone melatonin (Brzezinski, 1997), which may also play immunomodulating effects (Maestroni, 1993). Therefore, further randomized studies with arabinoxylan alone versus arabinoxylan plus melatonin will be required to better define the immunomodulating action of arabinoxylan. If further clinical and experimental studies will confirm the inhibitory action of arabinoxylan on T reg cell system, it could be included in cytokine-based immunotherapies to enhance their efficacy by counteracting T reg cell generation.

References
Atzpodien J, Kirchner H (1990) Cancer, cytokines and cytotoxic cells:interleukin-2 in the immunotherapy of human neoplasms. Klin Wochenschr 14, 1-10.
Banks RE, Patel PM, Selby PJ (1995) Interleukin-12:a novel clinical player in cytokine therapy. Br J cancer 71, 655-659.
Brzezinski A (1997) Melatonin in humans. N Engl J Med 336, 185-195.
Dieckmann D, Plottner H, Berchtold S, Berger T, Schuler G (2001) Ex vivo isolation and characterization of CD4+CD25+ T cells with regulatory properties from human blood. J Exp Med 193, 1303-1310.
Ghoneum M (1998) Enhancement of human natural killer cell activity by modified arabinoxylane fro rice bran(MGN-3). Int J Immunother 14, 89-99.
Ghoneum M, Gollapudi S (2005) Synergistic of arabinoxilan rice bran (MGN-3/Biobran in S. Cerevisiae-induced apoptosis of monolayer breast cancer MFC-7 cells. Anticancer Res 25(6B), 4187-96.
Ghoneum M, Brown J, Gollapudi S (2007) Yeast therapy for the treatment of cancer and its enhancement by MGN-3/Biobran, an arabinoxylan rice bran. Cellular Signaling and Apoptosis Research (Ed. Alex R. Demasi) Cap IV: 185-200.
Ghoneum M, Jewett A (2000) Production of tumor necrosis factor-alpha and interferon-gamma from human peripheral blood lymphocytes by MGN-3, a modified arabinoxylan from rice bran, and its synergy with interleukin-2 in vitro. Cancer Detect Prevent 24, 314-324.
Lissoni P, Giani L, Zerbini S, Trabattoni P, Rovelli F (1998) Biotherapy with the pineal immunomodulating hormone melatonin versus melatonin plus Aloe vera in untreatable advanced solid neoplasms. Nat Immun 16, 27-33.
Maestroni JGM (1993) The immunoneuroendocrine role of melatonin. J Pineal Res 14, 1-10.
Markus J, Miller A, Smith M, Orengo I (2006) Metastatic hemangiopericytoma of the skin treated with wide local excision and MGN-3. Dermatol Surg 32, 145-147.
Matsuda T, Hirano T (1990) Interleukin-6 (IL-6). Biotherapy 2, 363-371.
Moore KW, O’Garra A, De Waal-Malefyt R (1993) Interleukin-10. Ann Rev Immunol 11, 165-174.
Rosenberg SA (1992) The immunotherapy and gene therapy of cancer. J Clin Oncol 10, 181-191.
Shevach EM (2002) CD4+CD25+ suppressor T cells:more questions than answers. Nat Rev Immunol 2, 389-400.
Whittington R, Faulds D (1993) Interleukin-2. Drugs 46, 446-514.
Yang JC, Hughes M, Kammula U, Royal R, Sherry RM, Topalian SL, Suri KB, Levy C, Allen T, Mavroukakis, Lowy I, White DE, Rosenberg SA (2007) Ipilimubab (anti-CTLA4 antibody)causes regression of metastatic renal cell cancer associated with enteritis and hypophysitis. J Immunother 30, 825-830.
(download PDF version)


A clinical study of T-regulatory lymphocyte function in cancer patients in relation to tumor histotype, disease extention, lymphocyte subtypes and cortisol secretion

Research Article (download PDF version)

Luigi Vigorè1, Fernando Brivio2, Luca Fumagalli2, Roberto Vezzo1, Giusy Messina6, Franco Rovelli6, Massimo Colciago3, Giovanna D’Amico4, Giuseppe Di Fede5, Paolo Lissoni6

1 Laboratory of Immunomicrobiology, St.Gerardo Hospital, Monza, Milan, Italy
2 Division of Surgery, St.Gerardo Hospital, Monza, Milan, Italy
3 I.N.R.C.A Laboratory of Analyses, Casatenovo, Lecco, Italy
4 Research Center “Fondazione Tettamanti” Clinica Pediatrica Università Milano-Bicocca, Italy
5 Institute of Biological Medicine, Milan, Italy
6 Division of Radiation Oncology, St.Gerardo Hospital, Monza, Milan, Italy

*Correspondence: Dr. Paolo Lissoni, Divisione di Radioterapia Oncologica, Ospedale S.Gerardo, 20052 Monza, Milano, Italy; Fax: +390392332284, E-mail: p.lissoni@hsgerardo.org
Key words: Anticancer immunity, immunosuppression, T regulatory lymphocytes
Abbreviations: cytotoxic T lymphocyte-associated antigen-4, (CTLA-4); glucocorticoid-induced TNF-α receptor, (GITR); myeloidderived suppressor cells, (MDSC); NK cells, (CD16CD56); T cytotoxic lymphocytes, (CD8); T helper lymphocytes, (CD4); Tregulatory lymphocytes, (T-reg)

Received: 24 July 2008; Revised: 11 September 2008
Accepted: 12 September 2008; electronically published: October 2008

Summary

Several clinical investigations showed that the immune status is a prognostic variable in cancer patients, even tough the evaluation of the anticancer immunity is not generally considered in the medical oncology. Several immune parameters, including lymphocyte subsets and cytokine blood concentration, had been proposed to quantify the functional status of the anticancer immunity, but recent discoveries would suggest that the end-result of the various immune interactions is represented by a subtype of CD4 lymphocytes capable of suppressing the antitumor immune reaction, the so called T-regulatory lymphocytes (T-reg). This study was performed to detect T-reg count and percentage in solid tumor patients, in relation to tumor histotype, disease extension, lymphocyte sub-populations and cortisol circadian secretion. The study included 114 consecutive cancer patients affected by the most frequent tumor histotypes, 69 of whom showed a metastatic disease. In each patient we evaluated T-reg cells, identified as CD4+CD25+, in relation to T helper (CD4), T cytotoxic (CD8) and NK (CD16CD56) cells. Abnormally high values of T-reg cells were seen in 52/114 (46%) patients, and the percentage of high values of T-reg was significantly higher in metastatic patients than in non-metastatic ones. In contrast, no significant difference was seen in relation to tumor histotype. Patients with increased T-reg count had a significantly lower NK cell number. Finally no significant difference in T-reg number was seen between patients with altered or normal rithm of cortisol. The study confirmed that, irrespectively of tumor histotype the metastatic disease is associated with a progressive and increased T-reg generation, with a following suppression of anticancer immunity.

I. Introduction
At present, there is no doubt about the existence of a sub-type of T lymphocytes, the so-called T regulatory lymphocytes (T-reg), capable of suppressing the cellular immune responses,including the anticancer immunity (Thomton and Shevach, 2000; Shevach, 2002; von Herrath and Harrison, 2003; Schwartz, 2005; von Boehmer, 2005; Ziegler, 2006; Zou, 2006). However, the exact definition
of T-reg cells in terms of cell surface marker expression still remains controversial, particularly from a clinical point of view. All authors are in agreement to consider Treg lymphocytes as CD4+CD25+ cells, but at present it is still unknown whether the expression of CD4 and CD25 antigens may be sufficient to identify T-reg cells (Thomton and Shevach, 2000; Shevach, 2002; von Herrath and Harrison, 2003; Schwartz, 2005; von Boehmer, 2005; Ziegler, 2006; Zou, 2006), since several authors retain that the intracytoplasmatic expression of the FOX p3 protein is essential for the differentiation into T-reg cells (Ziegler, 2006; Zou, 2006).Recently, however, some preliminary observations would suggest that the cytoplasmatic expression of FOX p3 by CD4+CD25+ cells may be associated at least in some experimental conditions with a diminished, rather than with an enhanced immunosuppressive activity of T-reg cells (Siddiqui et al, 2007). In contrast, all authors agree that the expression of CD152 antigen, also called cytotoxic T lymphocyteassociated antigen-4 (CTLA-4) (Vasu et al, 2004), is fundamental for the immunosuppressive activity of T-reg cells (Takahashi et al, 2000), since the block of its expression by using anti-CTLA-4 monoclonal antibodies may abolish the suppressive activity of T-reg cells, with a following stimulation of the anticancer immunity in cancer patients (Knutson and Disis, 2007) and an enhanced incidence of autoimmune diseases in the healthy subjects (Lan et al, 2005). Therefore, the addition of a third marker, such as CD152 antigen, may allow to define a more homogeneous cell population provided by a regulatory activity with respect to the simple CD4+CD25+ expression (Dieckmann and Plottner, 2001). In fact, the suppressive regulatory action of CD4+CD25+CD152+ has appeared to be clearly higher than that played by the simple CD4+CD25+ T lymphocytes (Leong et al, 2006).This finding is not surprising, since the simple expression of CD25 marker, corresponding to the !-chain of IL-2 receptor, is not an exclusive characteristic of T-reg lymphocytes, but it is a non-specific property of the overall activated T lymphocytes (Thomton and Shevach, 2000; Shevach, 2002; von Herrath and Harrison, 2003; Schwartz, 2005; von Boehmer, 2005; Ziegler, 2006; Zou, 2006). At present, preliminary clinical studies would show that the percent of circulating CD4+CD25+ cells may be about 10% of the all CD4+ lymphocytes, and that of CD4+CD25+CD152+ cells may be about 40% of the total CD4+CD25+ cells, then the expected percent of CD4+CD25+CD152+ in the healthy subjects would be less than 5% of the total circulating CD4+ lymphocytes (Jago et al, 2004). Finally, the expression of glucocorticoidinduced TNF-α receptor (GITR) is also associated with an evident suppressive activity by T-reg lymphocytes (Kanamaru et al, 2004), which in fact are stimulated by
cortisol (Sthephens et al, 2004), that in contrast may inhibit the activity of the most other T lymphocytes, namely that of T helper lymphocytes, with a following diminished production of IL-2 (Claman, 1998). As far as the mechanisms responsible for T-reg-induced suppression of the anticancer immunity are concerned, several experimental observations have shown that T-reg cells may suppress the antitumor immune response through the release of immunosuppressive cytokines, namely IL-10 and TGF-β (Dieckmann et al, 2002), even though other authors would suggest that the suppressive activity of Treg cells on CD4+ and CD8+ lymphocyte activation may be relatively independent from the action of cytokines, by mainly requiring cell surface contact (Birebent et al, 2004). IL-2 has been proven to be essential for T-reg generation and some authors consider IL-2 as the main growth factor of T-reg lymphocytes (Antony and Restito, 2005), but more adequate studies have demonstrated that IL-2 may induce both stimulation and inhibition of T-reg generation and activation (Malek and Bayer, 2004). In fact, IL-2 has appeared to induce and promote T-reg differentiation only in the presence of TGF-β (Chen et al, 2003). Therefore, IL-2 would constitute the main human cytokine in influencing the characteristics of the anticancer immunity, since it may be responsible for both activation and suppression of an effective immune response against cancer cell proliferation and dissemination (Wang et al, 2001), namely depending on the whole status of the cytokine network, in particular on the presence or in the absence of adequate concentrations of TGF-β. In the absence of TGF-β, IL-2 stimulates the anticancer immunity, whereas it counteracts the generation of an effective antitumor immunity in the presence of TGF-β. In other words, IL-2 would physiologically control both tolerance and immunity, depending on the presence of TGF-β and other less known factors (Annunziato et al, 2002). In fact, under cancer immunotherapy with IL-2 the percent of T-reg cells has been shown to decrease in responding patients and to enhance in those with disease progression (Cesana et al, 2006). However, the regulation of T-reg functions does not depend only on immune factors, since it is also under a neuroendocrine control (Ji et al, 2004). In particular, cortisol has appeared to stimulate T-reg cell generation (Ji et al, 2004), with a following enhanced release of IL-10, by representing the main mechanism responsible for cortisol-induced immunosuppression. From a clinical oncological point of view, preliminary observations showed an enhanced percent of circulating CD4+CD25+ lymphocytes in cancer patients, namely in those with advanced disease (Sasada et al, 2003). The present study was performed to better establish which is T-reg behaviour in cancer patients in relation to both tumor histotype and disease extension.

II. Materials and methods
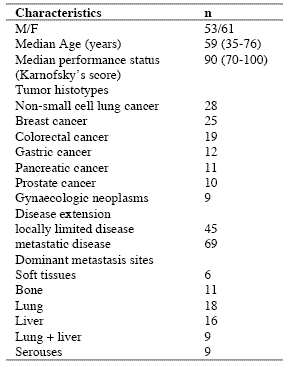
The study included 114 consecutive solid tumor patients with locally limited or metastatic disease, whose clinical characteristics are shown in Table 1. Lung cancer and gastrointestinal tumors were the most frequent neoplasms in our patients. For the immune detections, venous blood samples were collected in the morning after an overnight fast. Operable patients and metastatic patients were investigated before the surgical operation and before the onset of chemotherapy, respectively, in an attempt to exclude the possible influence of the various anticancer therapies on the immune status of patients.

In each sample, we have evaluated total lymphocyte count and the various lymphocyte subpopulations by a flow cytometric assay and monoclonal antibodies, including T helper lymphocytes (CD4), T cytotoxic lymphocytes (CD8), NK cells (CD16CD56), and T regulatory (T-reg) lymphocytes (CD4CD25). Normal values (95% confidence limits) of T-reg observed in our laboratory were below 240/mm3. Moreover, because of its importance in regulating lymphocyte functions and proliferation (Claman, 1998; Sthephens et al, 2004), the circadian rhythm of cortisol was also investigated by collecting blood samples at 8.00 A.M. and at 4.00 P.M., and cortisol serum concentrations were measured in duplicate by using the ECLA method. Data were reported as mean +/- SE, and statistically analyzed by the Student’s t test, the analysis of variance and the chi-square test, as appropriate.

III. Results
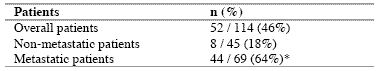
As reported in Table 2, an abnormally high number of T-reg was seen in 52/114 (46%) patients. Moreover, the percentage of cases with elevated number of T-reg observed in metastatic patients was significantly higher with respect to that found in non-metastatic patients (44/69 (64%) vs 8/45(18%), p < 0.01). Table 3 shows the mean number of T-reg and the mean percentages of T-reg with respect to both total lymphocytes and T helper (CD4+) lymphocytes observed in cancer patients in relation to their disease extension. The mean number of T-reg observed in metastatic patients was higher with respect to that found in patients with locally limited disease, without, however statistically significant differences. In contrast, the mean percentages of T-reg with respect to that of both lymphocytes and CD4 cells were significantly higher in metastatic patients than in the non-metastatic ones (p< 0.05 and p< 0.001,respectively). Moreover, within the metastatic group, patients with a normal lymphocyte count greater than 1500/mm3 showed a significantly higher mean number of T-reg with respect to the non-metastatic patients, whereas no difference was seen between nonmetastatic patients and metastatic patients with lymphocytopenia, consisting of lymphocyte count lower than 1500/mm3. In contrast, the mean percentages of T-reg with respect to total lymphocytes and CD4+ cells observed in both groups of metastatic patients with normal or low total lymphocyte count were significantly higher than in non-metastatic patients (lymphocytes: p< 0.025, CD4+ cells: p< 0.001).

Table 1. Clinical characteristics of 114 solid tumor patients
090722_clinicalstud1

Table 2. Percentages of abnormally high values of CD4+CD25+ lymphocytes
090722_clinicalstud2

* P < 0.01 vs non-metastatic patients

Table 3. Mean number of CD4+CD25+ lymphocytes and their mean percentages with respect to total lymphocytes and CD4+ lymphocytes in metastatic and non-metastatic patients
090722_clinicalstud3

* p<0.05 vs non-metastatic patients; ** p<0.025 vs non-metastatic patients; *** p<0.01 vs non-metastatic patients; **** p<0.001 vs nonmetastatic patients

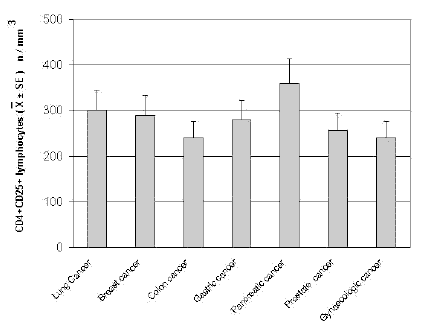
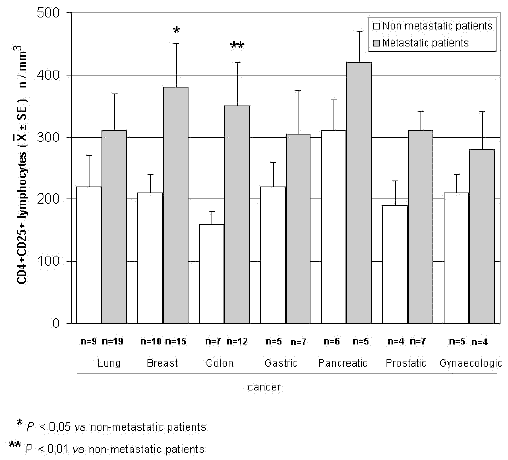
The mean counts of NK and CD8 cells in relation to that of T-reg are reported in Table 4. As shown, no significant difference in the mean number of CD8 lymphocytes was found between patients with normal or abnormally elevated number of T-reg. On the contrary, patients with elevated number of T-reg showed a significantly lower number of NK cells with respect to that found in those with normal T-reg count. Finally, Table 5 shows the circadian rhythm of cortisol in relation to total lymphocytes, CD4+ cells and T-reg mean number. A normal cortisol rhythm, with morning values greater at least than 50% with respect to the values occurring during the afternoon, was found in 85/114 (75%). Total lymphocyte and CD4+ cell mean numbers observed in patients with altered cortisol rhythm were significantly lower than those found in patients with normal cortisol circadianicity (p<0.01), whereas no significant difference was seen in the mean number of T reg. Figure 1 and Figure 2 illustrate T-reg mean numbers in relation to tumor histoptypes in the overall patients and with respect to their disease extension, respectively. No significant difference was seen in relation to tumor histotype. The highest values of T-reg were observed in pancreatic cancer patients, without however significant differences with respect to the overall other histotypes. The metastatic disease was associated with a higher number of T-reg with respect to the non-metastatic group in all tumor histotypes, even though a statistically significant differences occurred for the only breast cancer (p<0.05) and colorectal cancer (p< 0.01).

Table 4. Mean values of NK cells and CD8+ lymphocytes in cancer patients with normal or abnormally high values of CD4+CD25+ lymphocytes
090722_clinicalstud4

* p<0.05 vs normal values of CD4+CD25+ lymphocytes

Table 5. Mean numbers of total lymphocytes, T helper (CD4+) lymphocytes and T regulator lymphocytes (CD4+CD25+) in relation to cortisol circadian secretion in cancer patients
090722_clinicalstud5

* P<0.01 vs patients with altered cortisol rhythm
090722_clinicalstudfig1

Figure 1. CD4+CD25+ lymphocyte mean number in relation to tumor histotype
090722_clinicalstudfig2

Figure 2. CD4+CD25+ lymphocytes in relation to tumor histotype in metastatic and non-metastatic cancer patients

IV. Discussion
According to previous preliminary clinical investigations (Sasada et al, 2003; Cesana et al, 2006), this study confirms in a greater number of cancer patients that the metastatic disease is characterized by the evidence of an abnormally increased percentage of T-reg lymphocytes with respect to both total circulating lymphocytes and CD4+ lymphocytes. This finding does not seem to represent a specific characteristic of some tumor histotypes, then it could constitute a general alteration occurring during the progression of the neoplastic disease, by representing a fundamental immune parameter of cancer-related immunosuppression.

Several immune molecules have appeared to suppress the anticancer immunity, namely IL-6, IL-10, IL-1, TNF-α and TGF-β, but it seems that the common end result of their mechanisms of action may be represented by the stimulation of T-reg generation, with a consequent inhibition of the activation of an effective anticancer immune reaction. On the same way, several immune cells are able to suppress the anticancer immunity, including macrophages, T helper-2 lymphocytes and some myeloidderived suppressor cells, but also in this case they would act in a suppressive way by promoting the generation of Treg.

Then, the detection of T-reg amounts in terms of both absolute number and percentages with respect to total lymphocytes and CD4+ cells could constitute a simple and adequate clinical immune parameter to quantify the whole status of the anticancer immunity in the single cancer patient. Moreover, future clinical studies will be required to establish the possible prognostic significance of changes in T-reg percentage and number in relation to the anticancer efficacy of the various standard antitumor therapies. Moreover, it has to be remarked that T-reg lymphocytes would not represent the only immune cells involved in the suppression of the anticancer immunity. In fact, there is at least another fundamental immunosuppressive system, consisting of the monocytemacrophage cell lineage (Sica and Bronte, 2007). In more detail, it has been observed that the bone marrow may release myeloid precursors provided by suppressive activity on the antitumor immune response and defined as myeloid-derived suppressor cells (MDSC) (Kusmartsev and Gabrilovich, 2005). These cells have appeared to be characterized by the cell surface expression of GR-1, CD11b and CD80 antigens (Anderson et al, 2002; van Ginderachter et al, 2006). The myeloid suppressor cells would promote the generation and activation of T-reg lymphocytes, which at the other side would stimulate MDSC release from the bone marrow and M2 macrophage differentiation (Terabe et al, 2003; Wie et al, 2006).

Moreover, the myeloid suppressive cells would inhibit the anticancer immunity by promoting macrophage differentiation into the M2 sub-type (Ikemoto et al, 2003), which plays a clear inhibitory effect on the anticancer immunity, namely through the release of IL-6 (Ueno et al, 2000), whereas the M1 macrophage sub-type may either stimulate or suppress the antitumor immunity (Mantovani et al, 2004). M1 and M2 macrophage sub-types have appeared to be characterized by a high production of IL-12 or IL-10, respectively (Ueno et al, 2000).

Then, further studies by concomitantly evaluating T reg and MDSC count, will contribute to better define the immune mechanism responsible for the suppression of the anticancer immunity.

References
Anderson CF, Gerber JS, Mosser DM (2002) Modulating macrophage function with IgG immune complexes. J Endotoxin Res 8, 477-81.

Annunziato F, Cosmi L, Liotta F, Lazzeri E, Manetti R, Vanini V, Romagnani P, Maggi E, Romagnani S (2002) Phenotype,localization and mechanism of suppression of CD4+CD25+ human thymocytes. J Exp Med 196, 379-87.

Antony PA, Restito NP (2005) CD4+CD25+ T regulatory cells,immunotherapy of cancer,and interleukin-2. J Immunother 28, 120-8.

Birebent B, Lorho R, Lechartier H, de Guibert S, Alizadeh M,
Vu N, Beauplet A, Robillard N, Semana G (2004) Suppressive properties of human CD4+CD25+regulatory T cells are dependent on CTLA-4 expression. Eur J Immunol 34, 3485-96.

Cesana GC, DeRaffele G, Cohen S, Moroziewicz D, Mitcham J, Stoutenburg J, Cheung K, Hesdorffer C, Kim-Schulze S, Kaufman HL (2006) Characterization of CD4+CD25+ regulatory T cells in patients treated with high-dose interkleukin-2 for metastatic melanoma or renal cell carcinoma. J Clin Oncol 24, 1169-77.

Chen W, Jin W, Hardegen N, Lei KJ, Li L, Marinos N, McGrady G, Wahl SM (2003) Conversion of peripheral CD4+CD25- naïve T cells to CD4+CD25+ regulatory T cells by TGF-β induction of transcription factor Foxp 3. J Exp Med 198, 1875-86.

Claman HN (1998) Corticosteroids and the immune system. Adv Exp Med Biol 245, 203-10.

Dieckmann D, Bruett H, Ploettner H, Lutz MB, Schuler G (2002) Human CD4+CD25+ regulatory contact-dependent T cell induce IL-10 producing,contact-independent type-1-regulatory T cells. J Exp Med 196, 247-53.

Dieckmann D, Plottner H (2001) Ex vivo isolation and characterizationof CD4+CD25+ T cells with regulatory properties from human blood. J Exp Med 193, 1303-10.

Ehrke MJ, Mihich E, Berd D, Mastrangelo MJ (1989) Effects of anticancer drugs on the immune system. Semin Oncol 16, 230-9.

Ghiringhelli F, Larmonier N, Schmitt E, Parcellier A, Cathelin D, Garrido C, Chauffert B, Solary E, Bonnotte B, Martin F (2004) CD4+ CD25+ regulatory T cells suppress tumor immunity but are sensitive to cyclophosphamide which allows Immunotherapy of established tumors to be curative. Eur J Immunol 34, 336-44.

Ikemoto S, Yoshida N, Narita K, Wada S, Kishimoto T, Sugimura K, Nakatani T (2003) Role of tumor-associated macrophages in renal cell carcinoma. Oncol Rep 10, 1843-9.

Jago CB, Yates J, Camara NOS, Lechler RI, Lombardi AG (2004) Differential expression of CTLA-4 among T cell subsets. Clin Exp Immunol 136, 463-71.

Ji HB, Liao G, Faubion WA, Abadía-Molina AC, Cozzo C, Laroux FS, Caton A, Terhorst C (2004) Cutting edge, the natural ligand for glucocorticoid-induced TNF receptorrelated protein abrogates regulatory T cell suppression. J Immunol 172, 5823-7.

Kanamaru F, Youngnak P, Hashiguchi M, Nishioka T, Takahashi T, Sakaguchi S, Ishikawa I, Azuma M (2004) Costimulation via glucocorticoid-induced TNF receptor in both conventional and CD25+ regulatory CD4+ T cells. Immunol 172, 7306-14.

Knutson KL, Disis M, Salazar L (2007) CD4 regulatory T cells in human cancer pathogenesis. Cancer Immunol Immunother 556, 271-85.

Kusmartsev S, Gabrilovich DI (2005) STAT1 signaling regulates tumor-assolciated macrophage-mediate T cell deletion. J Immunol 174, 4880-91.

Lan RY, Ansari AA, Lian ZX, Gershwin ME (2005) Regulatory T cells, development,function,and role in autoimmunity. Autoimmun Rev 4, 351-63.

Leong PP, Mohammad R, Ibrahim N, Ithnin H, Abdullah M, Davis WC, Seow HF (2006) Phenotyping of lymphocytes expressing regulatory and effector markers in infiltrating ductal carcinoma of the breast. Immunol Lett 102, 229-36.

Malek TR, Bayer AL (2004) Tolerance not immunity crucially depends on IL-2. Nat Rev Immunol 4, 665-74.

Mantovani A, Sica A, Sozzani S, Allavena P, Vecchi A, Locati M (2004) The chemokine system in diverse forms of macrophage activation and polarization. Trends Immunol 25, 677-86.

Sasada T, Kimura M, Yoshida Y, Kanai M, Takabayashi A (2003) CD4+CD25+ regulatory T cells in patients with gastrointestinal malignancies, possible involvement of regulatory T cells in disease progression. Cancer 98, 1089-93.

Schwartz RH (2005) Natural regulatory T cells and selftolerance. Nat Immunol 6, 327-30.

Shevach EM (2002) CD4+CD25+ suppressor T cells, more questions than answers. Nat Rev Immunol 2, 389-400.

Sica A, Bronte V (2007) Altered macrophage differentiation and immune dysfunction in tumor development. J Clin Invest 117, 1155-66.

Siddiqui SA, Frigola X, Bonne-Annee S, et al (2007) Tumorinfiltrating Foxp3 CD4+CD25+ T cells predict poor survuival in renal cell carcinoma. Clin Cancer Res 13, 2075-81.

Stephens GL, McHugh RS, Whitters MJ, Young DA, Luxenberg D, Carreno BM, Collins M, Shevach EM (2004) Engagement of glucocorticoid-induced TNFR family-related receptor on effector T cells by its ligand mediates resistance to suppression by CD4+CD25+ T cells. J Immunol 173, 5008-20.

Takahashi T, Tagami T, Yamazaki S, Uede T, Shimizu J, Sakaguchi N, Mak TW, Sakaguchi S (2000) Immunologic and tolerance maintained by CD25+CD4+ regulatory T cells constitutively expressing cytotoxic T lymphocyte-associated antigen. J Exp Med 192, 1285-94.

Terabe M, Matsui S, Park JM, Mamura M, Noben-Trauth N, Donaldson DD, Chen W, Wahl SM, Ledbetter S, Pratt B, Letterio JJ, Paul WE, Berzofsky JA (2003) Transforming growth factor-β production and myeloid cells are an eggector mechanism trhough which CD1d-restricted T cells block cytotoxic T lymphocyte-mediated tumor immunosurveillance, abrogation prevents tumor recurrence. J Exp Med 198, 1741-52.

Thomton AM, Shevach EM (2000) Suppressor effector function of CD4+CD25+ immunoregulatory T cells is antigen nonspecific. J Immunol 164, 183-90.

Ueno T, Toi M, Saji H, Muta M, Bando H, Kuroi K, Koike M, Inadera H, Matsushima K (2000) Significance of macrophage chemo-attractant protein-1 in macrophage recruitment,angiogenesis and survival in human breast cancer. Clin Cancer Res 6, 3282-9.

Van Ginderachter JA, Movahedi K, Hassanzadeh Ghassabeh G, Meerschaut S, Beschin A, Raes G, De Baetselier P (2006) Classical and alternative activation of mononuclear phagocytes, picking the best of both worlds for tumor promotion. Immunobiology 211, 487-501.

Vasu C, Prabhakar BS, Holterman MJ (2004) Targeted CTLA-4 engagement induces CD4+CD25+CTLA-4 high T regulatory cells with target alloantigens specificity. J Immunol 173, 2866-76.

von Boehmer H (2005) Mechanisms of suppression by suppressor T cells. Nat Immunol 6, 338-44.

von Herrath MG, Harrison LC (2003) Regulatory lymphocytes, antigen-induced regulatory T cells in autoimmunity. Nat Rev Immunol 3, 223-32.

Wang XB, Zheng CY, Giscombe R, Lefvert AK (2001) Regulation of surface and intracellularexpression of CTLA-4 on human peripheral T cells. Scand J Immunol 54, 453-8.

Wie S, Kryczeck I, Zou W (2006) Regulatory T-cell compartmentalization and trafficking. Blood 108, 426-31.

Yang R, Cai Z, Zhang Y, Yutzy WH 4th, Roby KF, Roden RB (2006) CD80 in immune suppression by mouse ovarian carcinoma-associated Gr-1+CD11b+ myeloid cells. Cancer Res 66, 6807-15.

Ziegler SF (2006) FOXP3 of mice and men. Annu Rev Immunol 24, 209-26.

Zou W (2006) Regulatory T cells, tumour immunity and immunotherapy. Nat Rev Immunol 6, 295-307.

(download PDF version)


La terapia con campi magnetici è tradizionalmente usata per patologie ortopediche; negli ultimi anni alcuni studi hanno dimostrato l’utilità anche in altre patologie ed in particolare quelle di pertinenza neurologica.

Nel nostro Istituto dal 2001 il trattamento con campi elettromagnetici di bassa ed alta frequenza viene utilizzata singolarmente o in associazione con trattamenti farmacologici in varie situazioni. Lo scopo della relazione è di illustrare tre casi clinici in cui la terapia con campi elettromagnetici a frequenza ultrabassa si è dimostrata efficace; la tecnologia utilizzata è la risonanza ciclotronica endogena.

Per tutti i casi lo schema terapeutico prevedeva 2 frazioni settimana della durata di 30 minuti ciascuna per un totale di 12 sedute con una valutazione clinica a metà trattamento.

Primo caso: uomo di 41 anni con diagnosi radiologica di sclerosi multipla (luglio 2003-lesioni all’encefalo e midollo spinale); gli esami evidenziarono alti valori di stress ossidativo.

La sintomatologia consisteva in dolori in sede cervicale e lombare e un moderato deficit motorio dell’arto inferiore destro.
Trattamento terapeutico: trattamento con prodotti antiossidanti e terapia con campi elettromagnetici con frequenza variabile da 10 a 30 Hz e intensità variabile tra 10 e 25 microTesla.
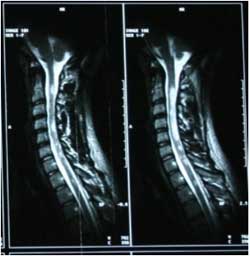
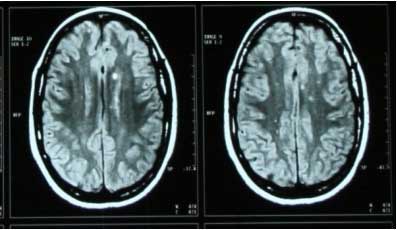
Al termine del trattamento si era verificato un significativo miglioramento dei sintomi; la RM di controllo ha evidenziato una riduzione del numero e dimensioni delle lesioni attive. Tale quadro si mantiene anche alla ultima RM(febbraio 2007)

Secondo caso: donna di 23 anni con quadro radiologico (RM 2005)di sclerosi multipla e lesioni encefaliche e midollari con importanti deficit motori neurologici;gli esami evidenziarono alti livelli di stress ossidativo; la paziente era in cura con Interferone da un anno con malattia stabile.
0801_1
0801_2

Trattamento terapeutico:campi elettromagnetici con frequenza variabile tra 10 e 20 Hz e intensità variabile tra 20 e 30 microTesla;come terapia di supporto trattamento energico con prodotti antiossidanti.
L’ultima RM(dicembre 2006) ha mostrato una significativa riduzione delle lesioni ed in particolare modo di quelle midollari.
0801_4
0801_3

Terzo caso: uomo di 70 anni con broncopneumopatia cronica severa( stadio III Gold) in cura da alcuni anni con broncodilatatori e steroidi associata disfunzione sistodiastolica ventricolare sinistra.
I sintomi più evidenti erano la dispnea ed episodi continui di apnea notturna che limitavano molto la qualità di vita.
Dopo cinque sedute con campi elettromagnetici il paziente riferiva un notevole miglioramento della quantità e qualità del sonno e seppure meno evidente anche della dispnea.
La frequenza era di 40-45 Hz con una intensità tra 70 e 90 microTesla.
Alla fine del ciclo di terapia era ben evidente un miglioramento dei parametri respiratori ed anche della qualità di vita. La malattia era radiologicamente stabile.

In tutti e tre i casi riportati l’aggiunta di campi elettromagnetici al trattamento farmacologico ha evidenziato un miglioramento della qualità di vita con quadro radiologico di regressione in 2 casi e stabilità nel terzo.
In considerazione degli aspetti prognostici,psicologici e socioeconomici di queste patologie a nostro avviso è un risultato importante.
Oltretutto il trattamento con campi elettromagnetici è stato ben tollerato e senza effetti collaterali.
Pertanto riteniamo che la terapia con campi elettromagnetici a frequenza ultrabassa possa rappresentare una valida opzione in associazione con altri presidi in una strategia terapeutica integrata; inoltre la possibilità di eseguire eventualmente il trattamento a domicilio risulta particolarmente interessante.

Comunque,in futuro è auspicabile la costituzione di adeguati studi clinici controllati al fine di approfondire in maniera sempre più dettagliata gli aspetti concernenti i parametri tecnici,la sinergia con altre terapie e l’interazione con tessuti biologici.

del Prof. Giuseppe di Fede e Marco G. M. Mancuso

da ELECTROMAGNETIC BIOLOGY AND MEDICINE Volume 26, Numero 4 Anno 2007


Gennaio 30, 2013 Newsletter

Lo stato di salute del nostro organismo dipende da molteplici fattori ed esso si riflette in misura rilevante sul nostro atteggiamento posturale.Intervenendo sulla postura si facilita il nostro stato di equilibrio psicofisico e si favorisce una miglior funzionalità di tutto il corpo, di conseguenza una ottimale applicazione del principio di auto guarigione.

La postura può essere influenzata da fattori strutturali, emotivi, energetici, viscerali, tra loro correlati.
Le cause strutturali possono essere determinate da problemi della vista, da malocclusione, dall’appoggio podalico, disfunzioni a carico degli
arti; tutto questo influisce sulla colonna vertebrale che può essere la causa o l’effetto di tali disfunzioni. Un attenta analisi obiettiva, avvalendosi di test kinesiologici, supportati dai dati forniti da una pedana podobarometrica, è in grado di fornire al medico, anche specialista (non focalizzato ad una visione settoriale del problema e dell’organismo), importanti dati sull’origine del problema primario e indirizzare la terapia in modo mirato. Senza ricorrere, se non in casi di effettiva necessità, ad indagini più impegnative ed invadenti.

Il medico ginecologo può sostenere la propria paziente in stato di gravidanza, prevenendo problemi di larga diffusione per questo stato, quali la stipsi o la sciatalgia (spesso dovuti all’ assetto della colonna vertebrale), malesseri assai diffusi, causa di sofferenza diretta non solo per la futura mamma, ma anche per il bimbo che porta in grembo.
Alcune piccole disfunzioni, insignificanti in un periodo di normalità, tendono ad accentuarsi con il procedere della gravidanza e quindi del nuovo assetto posturale assunto dalla donna.

Il medico dentista o l’ortodontista, possono verificare quanto l’intervento da loro progettato possa o meno influire sulla postura del paziente e suggerirgli interventi collaterali di riequilibrio, prima di procedere con il proprio, qualora si rendesse necessario. Sono raccomandate tecniche innovative in tal senso che sfruttano la capacità recettoriale (i nostri sensori) invece della tradizionale vettoriale (forze, trazioni ecc.).

Il Fisiatra, il neurologo e il medico legale, possono usufruire degli importanti e precisi dati forniti dalla pedana baropodometrica, per le loro valutazioni sullo stato di equilibrio nei singoli casi, sia in posizione statica che deambulatoria.

L’ortopedico è quindi in grado di prescrivere ortesi plantari con la massima precisione e accuratezza nel non creare fastidiosi problemi di adattamento posturali collaterali.

L’ottico o l’oculista possono verificare se le disfunzioni visive sono primarie o conseguenti ad adattamenti compensatori di una postura non proprio in equilibrio.


Novembre 30, 2012 Newsletter

La gravidanza è uno stato particolare durante il quale tutto il metabolismo della donna va incontro a profonde modificazioni. È bene quindi provvedere con un cambiamento nutrizionale in grado di fornire il corretto apporto calorico e tutti i nutrienti necessari alla mamma e alla crescita del bambino.

Durante le visite di routine, peso e bilancia sembrano essere il fulcro cruciale per gran parte di medici e ginecologi. In realtà, accanto al capitolo del controllo del peso, si apre quello sul corretto apporto di macro e micronutrienti e quello riguardante la prevenzione di sindromi allergiche e intolleranze. Per il benessere di mamma e bambino è importante quanto la donna mangia, ma è fondamentale che cosa mangia. La gestazione deve essere un momento di “educazione alimentare” e non di “restrizione”.

Data la posta in gioco, la gravidanza può essere per la donna un’ottima occasione per acquisire nuove conoscenze in ambito nutrizionale come il corretto frazionamento dei pasti durante la giornata, il corretto apporto di tutti i macronutrienti (carboidrati, proteine, fibre, lipidi) e micronutrienti (sali minerali, vitamine) e la prevenzione di allergie e intolleranze.

L’aumento ponderale in gravidanza è strettamente correlato al peso pre-gravidico e al BMI (Boby Mass Index o Indice di Massa Corporea): un BMI corretto e nella norma lascia di solito ben sperare in un aumento di peso corretto rispetto a un BMI da sottopeso o sovrappeso. Nel primo trimestre, è previsto un aumento di peso di circa 2 kg, dal secondo trimestre il controllo deve essere più oculato e non deve essere superiore ai 500g settimanali onde evitare sofferenza fetale.

In generale evitare gli alcolici e limitare i “nervini” (caffè, tè, cacao) che stimolano la contrazione muscolare e quindi anche quella uterina.

E’ bene frazionare i pasti rispettando lo spuntino di metà mattina e metà pomeriggio così da evitare pasti abbondanti che possono aggravare sintomi quali gonfiore, nausea, vomito. Sempre per gli stessi motivi è consigliato evitare cibi “pesanti” quali fritti, piatti troppo conditi, grassi animali (lardo e pancetta), dolci a base di panna e burro. Nei casi di nausea e vomito evitare piatti in brodo, preferire una colazione salata a quella dolce, prediligere le verdure cotte e condimenti a base di limone (ricordiamo che la presenza di vitamina C favorisce l’assorbimento del ferro presente negli alimenti).

È consigliata la massima igiene alimentare e un’abbondante idratazione (2L di acqua al giorno).

Tenere presente l’aumento del fabbisogno nutrizionale e in particolare di vitamine, calcio, potassio, ferro, fosforo e acido folico; da qui l’importanza di un’alimentazione completa. Meglio sopperire a tale fabbisogno da fonti naturali (gli alimenti) prima che dagli integratori (per quanto riguarda l’acido folico, di cui gli alimenti sono poco ricchi, è bene assumere un integratore secondo indicazione medica). Si consiglia di accompagnare i pasti principali con una buona porzione di verdura (meglio se di stagione) e di assumere due porzioni di frutta al giorno. Frutta, verdura e legumi sono ricchi in micronutrienti. Prediligere, inoltre, i cibi integrali (il pane integrale ad esempio contiene sette volte più ferro di quello bianco).

Veniamo ora all’importanza di un’alimentazione sì equilibrata ma allo stesso modo “preventiva”, come già accennato, nei confronti di allergie e intolleranze alimentari. Ad esempio, nei casi di donne particolarmente allergiche, alcuni studi riportano una minore incidenza di forme allergiche ereditarie se, durante la gravidanza, la donna ha seguito un controllo nutrizionale atto a ridurre tutti i nutrienti che potrebbero far scaturire il problema già nel neonato. Preferire quindi alimenti “anallergici” quali carni bianche, pesce, riso, latte di capra, ecc. riducendo il consumo di latte vaccino e latticini, uova e alimenti molto allergenici (fragole, pesche, frutta secca, cacao, ecc.).

La nutrizione della donna gravida deve essere sì “libera” e a suo gusto secondo le cosiddette “voglie”, ma è comunque giusto attenersi a un profilo nutrizionale molto vario così da evitare, o accentuare, intolleranze alimentari nella mamma e quindi “accumuli” nel nascituro.

Se sospettate di essere intolleranti o se semplicemente volete assicurarvi di seguire un’alimentazione corretta anche per il vostro bambino, una buona idea potrebbe essere quella di eseguire il test ALCAT per le intolleranze alimentari. In seguito, un esperto potrà indicarvi il tipo di alimentazione più idonea per voi, così da evitare spiacevoli sintomi in un momento tanto atteso! L’ALCAT Test, diffuso da più di vent’anni e validato da numerosi studi condotti presso centri di ricerca (Fondazione IRCCS Policlinico San Matteo di Pavia, Laboratorio di Immuno-Allergologia, pubblicazioni sulla rivista ufficiale dell’European Academy of Allergology and Clinical Immunology), permette di seguire una terapia non farmacologica ma nutrizionale. Dopo una prima fase di eliminazione dei cibi risultati positivi al test, si procederà con la reintroduzione graduale e controllata di tutti gli alimenti.

In conclusione, oltre che per il rischio di aumento ponderale, il controllo dell’alimentazione della madre in gravidanza è importante per lo sviluppo del feto e per la prevenzione di allergie, intolleranze alimentari, dermatiti atopiche, bronchioliti, coliti, ecc., sintomi che possono presentarsi già dalle prime settimane di vita del bambino.

a cura della dr.ssa Jessica Barbieri, Biologa Nutrizionista, Consulente IMBIO – Istituto di Medicina Biologica Milano.


Ottobre 30, 2012 Newsletter

Dopo aver presentato pregi e difetti di “zucchero bianco, di canna e fruttosio“, (Come dolcificare nel modo migliore? – parte 1) proseguiamo la panoramica sui dolcificanti naturali e sintetici valutando: saccarina, aspartame, sucralosio e stevia.

SACCARINA: La saccarina è stata il primo dolcificante artificiale. La parola deriva dal latino e significa zucchero. È disponibile in tre forme: Acido Saccarinico, Saccarina di Sodio, Saccarina di Calcio. Quella più usata è la saccarina di sodio.

Ha un potere dolcificante 300 volte superiore al saccarosio, ma presenta un retrogusto leggermente amaro e metallico, generalmente considerato sgradevole specialmente ad alte concentrazioni. A differenza di simili composti di sintesi (es. aspartame), la saccarina è stabile al calore anche in ambiente acido, è inerte rispetto agli altri ingredienti alimentari e non richiede precauzioni di conservazione. Nei paesi in cui l’uso di entrambi i composti è consentito, la saccarina è spesso associata al Ciclammato in proporzioni 1:10 per correggere i citati difetti di retrogusto; è spesso associata anche all’aspartame.

Nel 1878 fu scoperta casualmente in un laboratorio, dove si lavorava il catrame. Fu una scoperta importante, soprattutto per i diabetici. Infatti, la saccarina transita attraverso l’apparato digerente senza alterare i livelli sanguigni d’insulina e in pratica senza fornire alcuna energia all’organismo.

Preoccupazione sulla potenziale nocività e cancerogenicità si espresse massimamente nel 1977, quando fu pubblicato un lavoro che comunicava l’aumento d’incidenza del cancro alla vescica in ratti alimentati con alte dosi di saccarina. Al momento, viste le bassissime quantità di utilizzo, non è stata dimostrata per tali quantità nessuna correlazione. La saccarina è impiegata in una grande varietà di cibi, bevande e cosmetici.

Non è metabolizzata dal nostro organismo; una volta assunta, è rapidamente assorbita (circa 90%) e come tale eliminata con le urine, senza subire modifiche. Non influenza i livelli glicemici e non fornisce alcuna energia all’organismo. Non favorisce la carie e quindi consigliata nelle diete ipocaloriche e nei diabetici. Restano, tuttavia, molti dubbi sulla tossicità, pur esistendo tantissimi studi che ne confermano la sicurezza per dosi di consumo normali. I dubbi circa il coinvolgimento della sostanza nei confronti del cancro alla vescica restano. Molta prudenza per l’uso in gravidanza, data la capacità di attraversare la placenta.

ASPARTAME: L’aspartame è un altro dolcificante artificiale. E’ composto da due aminoacidi, l’acido aspartico e la fenilalanina, più il metanolo che esterifica l’estremità carbossilica della Fenilalanina.

Pur avendo le stesse calorie dello zucchero, il suo potere dolcificante è 200 volte superiore; per questa ragione ne servono piccole quantità per dolcificare cibi e bevande.

Le persone che soffrono di fenilchetonuria (hanno difficoltà nell’assimilare la fenilalanina), devono limitare l’assunzione di questo dolcificante perché è fonte di fenilalanina.
L’utilizzo come dolcificante alimentare, con la sigla E 951, è autorizzato in dose massima giornaliera di 40 mg./Kg di peso. Esistono molte diatribe sul ruolo cancerogeno dell’aspartame (ci sono numerosi studi in merito). Nel 1980, un’inchiesta decretò la mancanza di dati sufficienti a confermare il legame tra aspartame e tumori al cervello.

Tuttavia, fu negata una nuova autorizzazione all’uso, in attesa di nuovi dati. Altri studi evidenziarono l’aumento dell’incidenza di linfomi e leucemie nei topi femmine a seguito dell’assunzione di vari dosaggi di aspartame. Inoltre, uno studio italiano ha confermato questi dati, e ha ipotizzato un legame tra formaldeide (il metabolismo dell’Aspartame, libera anche Metanolo, trasformato prima in Formaldeide e poi in Acido Formico, entrambi tossici) rilasciata dal metabolismo dell’aspartame e l’aumento di tumori cerebrali (Europee Journal of Oncology, del 2005). Entro settembre 2012, l’EFSA, la corrispondente europea dell’FDA americana, dovrà rivalutare la sicurezza dell’aspartame. Particolare importante: qualora sia presente un disturbo (potrebbero esisterne diversi), imputabile all’assunzione di aspartame, sono necessari 60 giorni senza assunzione di aspartame, per far regredire tale sintomatologia.

Uno dei più grossi limiti dell’aspartame è quello della non resistenza alle temperature (superiori ai 30°), quindi anche quella del corpo umano, che attiverebbe i processi che portano alla liberazione delle sostanze tossiche di cui parlavo prima. Per dovere d’informazione, riporto quali sono i punti a favore dell’aspartame che ne spingono l’utilizzo: basso potere calorico (essendo circa 200 volte più dolce del saccarosio) per cui ne servono piccolissime quantità; Non innalza la glicemia, per cui adatto ai diabetici, ma ricordiamo tutti i grossi dubbi ancora esistenti.

SUCRALOSIO: Diffuso da poco tempo, anche se scoperto in Inghilterra già nel 1976, questo dolcificante deriva dal saccarosio e, per le manipolazioni cui è sottoposto lo zucchero, è considerato un dolcificante artificiale.

E’ realizzato con un processo in più fasi, si parte dal classico zucchero da cucina, il saccarosio, cui sono sostituiti tre gruppi ossidrilici (formati da ossigeno e idrogeno) con tre atomi di cloro. Il risultato è un dolcificante stabile, con lo stesso sapore dello zucchero, ma senza calorie.

Dopo questa scoperta, il sucralosio, è stato sottoposto a un programma conclusivo di test sulla sicurezza per un periodo di 20 anni. Oggi il sucralosio, è autorizzato in oltre 80 paesi. Può essere utilizzato da tutti, anche da bambini, durante la gravidanza o l’allattamento, ed anche dai diabetici. Resiste al calore e può essere sottoposto a cottura, anche in forno. E’ molto utile per quanti cercano di ridurre l’assunzione di zucchero e calorie. Aumenta sempre più il numero di alimenti e bevande che sono dolcificate con sucralosio. Quello che rende possibile l’utilizzo in piccolissime quantità, è un potere dolcificante circa 600 volte superiore a quello dello zucchero.
Grosso vantaggio è l’eccellente sapore dolce, molto simile a quello dello zucchero.

Inizialmente vi fu un dubbio sul destino degli atomi di cloro, ma attendibili accertamenti hanno promosso a pieni voti questa sostanza. Infatti, il sucralosio rimane intatto nell’organismo. Il cloro non è liberato, dato che la molecola di sucralosio rimane intatta ed è eliminata quasi totalmente senza modifiche. Altro dato importante è che la molecola non interagisce minimamente con l’alimento che la contiene.

STEVIA: recentemente si è diffuso un nuovo dolcificante, che presenta interessanti caratteristiche: la stevia.

Si tratta di una piccola pianta erbacea arbustiva perenne della famiglia delle composite (lattuga, calendula, cicoria), nativa delle montagne fra Paraguay e Brasile. Ha una buona capacità dolcificante: nella sua forma naturale è circa 10/15 volte più dolce del normale zucchero da tavola. Nella sua forma più comune di polvere bianca, estratta dalle foglie della pianta, arriva a essere dalle 70 alle 400 volte più dolce dello zucchero, pertanto pare sia il dolcificante naturale più potente. Una sola fogliolina fresca dopo qualche istante, trasferisce al palato una forte sensazione dolce, lasciando alla fine un lieve retrogusto di liquirizia. I principi attivi sono lo Stevioside e il Rebaudioside A.

Non causa diabete; non ha calorie; non altera la glicemia; non dovrebbe avere tossicità (al contrario dei dolcificanti sintetici); non provoca carie; non contiene sostanze artificiali; può essere utilizzata per cucinare. Sono stati ipotizzati anche alcuni impieghi in medicina per il diabete e l’obesità. Consente, infatti, di ridurre il consumo di zucchero, specie quello bianco.

Si utilizza ormai su larga scala, in Giappone, per esempio, è già usata per dolcificare la Coca Cola Light.
La sua commercializzazione è stata a lungo ostacolata per via dei numerosi interessi legati alla produzione di altri dolcificanti ( barbabietole da zucchero, canna da zucchero ecc).

Importanti caratteristiche che la connotano sono:

  • Non è fermentabile (come lo zucchero), quindi utile a chi soffre di candida
  • Stabile al calore, almeno fino a 200° C
  • Non è tossica, quindi sicura
  • E’ senza calorie
  • Può essere utilizzata dai Diabetici e nelle diete ipocaloriche

È sicuramente un buon dolcificante naturale, già usato in molti paesi; per il momento i limiti sono dati dai costi, non ancora competitivi per la coltivazione delle piante e per l’estrazione.

Infine, per concludere questa panoramica sui dolcificanti (ricordo la prima parte dell’articolo: Come dolcificare nel modo migliore? – parte 1), vorrei esprimere solo una breve considerazione. Tra i vari dolcificanti, vale sempre la regola delle quantità, ad esempio, il fruttosio, entro limitate quantità, può essere utilizzato tranquillamente, ma aumentando il consumo crescono, in maniera direttamente proporzionale, gli svantaggi. Ricordo inoltre le virtù della stevia e del sucralosio, che veramente restano inerti e senza calorie.

a cura del Dr Francesco Lampugnani, Biologo Nutrizionista, Specialista in Farmacologia


Ottobre 30, 2012 Newsletter

Le proprietà nutritive del latte sono sempre state associate al concetto di salute e crescita, e il suo consumo è parte di una cultura popolare che si tramanda da generazioni.Si tratta, infatti, di un alimento indispensabile per il bambino in crescita. Per gli adulti il discorso è differente e per valutare gli effetti positivi del suo consumo dobbiamo considerare diversi aspetti. Primo fra tutti, la qualità del prodotto.

La gestione dell’allevamento delle mucche da latte è stata modificata nel tempo, con importanti conseguenze nelle proprietà e nella sicurezza dell’alimento: il latte che beviamo oggi ha una qualità inferiore rispetto a quella di tanti anni fa. Perché il latte sia di massima qualità, le mucche dovrebbero poter pascolare e alimentarsi in erba, libere di muoversi per tutto il giorno. Lo scenario può essere invece molto diverso: le mucche sono mantenute in batterie, con mangimi a base di soia, fieno e alimenti derivati. Non possono muoversi liberamente e passano gran parte del tempo a mangiare biada, sottoposte a stress produttivo con la somministrazione di fattori di crescita che aumentano la produzione di latte, anche di 4 o 5 volte in più rispetto alla normalità.

Il latte prodotto dalle mucche al pascolo sarà quindi più ricco di omega tre, antiossidanti naturali, proteine, calcio e minerali, mentre quello prodotto dalle mucche in batteria conterrà questi fattori nutritivi in quantità ridotta.

Altra importante considerazione riguarda la correlazione tra il consumo di latte e latticini nell’adulto e il rischio di contrarre patologie prostatiche, fino al cancro prostatico. [Torniainen S. et al Lactase persistence, dietary intake of milk, and the risk for prostate cancer in Sweden and Finland, Cancer epidemic, Bio makers e prevention, 2007, 16 (5), pp. 956-61].

Dall’altra parte però esiste anche un ruolo protettivo per il tumore al colon, data la presenza nel latte di una sostanza chiamata lattoferricina che deriva dalla digestione enzimatica della lattoferrina, nota per le proprietà anti cancro e immunostimolanti.

Nella donna, un elevato consumo di latte e latticini favorisce la produzione di cisti ovariche, seno fibromatoso e tumore al seno. Ecco perché le linee Guida della prevenzione anticancro, diffuse dai centri di terapia oncologica, sconsigliano il consumo di latte alle donne che hanno avuto un problema oncologico a seno, utero e ovaie.

Inoltre, Il 55% della popolazione mondiale è intollerante al lattosio, il principale zucchero del latte. Tuttavia, esiste una grande variabilità geografica: nei paesi dell’Europa settentrionale il 60-70% delle persone mantiene Ia funzione dell’enzima che digerisce il lattosio. Man mano che si scende dal nord Europa, invece, l’attività della lattasi si riduce: nella nostra penisola e dintorni, bacino del Mediterraneo, il deficit genetico per la Lattasi è molto frequente.

Come tutte in tutte le situazioni confuse, è importante non adottare concetti estremi e prese di posizione inutili. Forse basta una domanda molto semplice: abbiamo bisogno di grandi quantità di latte e prodotti lattiero caseari?
I bambini sì, è chiaro per tutti. Gli adulti no!

Infine, è importante ricordare che uno screening genetico può aiutarci a individuare le persone che possono trarre beneficio da un’alimentazione a base di prodotti lattiero caseari. La personalizzazione del consiglio nutrizionale, e il buon senso, ancora una volta, prevalgono sulle credenze popolari. Bisogna rivolgersi a uno specialista in nutrizione che possa avvalersi dell’indagine genetica, per meglio consigliare e educare non solo il singolo soggetto ma tutta la famiglia.


Settembre 30, 2012 Newsletter

Secondo una recentissima ricerca, condotta da un gruppo dell’Università di Adelaide, e pubblicata sull’ultimo numero dell’European Journal of Epidemiology, i bambini alimentati con diete sane in età precoce svilupperebbero, nel tempo, un quoziente intellettivo leggermente superiore, rispetto ai coetanei cresciuti con “diete spazzatura”.

Lo studio, che ha avuto come campione oltre 7.000 bambini, ha esaminato il legame tra le abitudini alimentari dei bambini a 6 mesi, 15 mesi e due anni, e il loro quoziente d’intelligenza (QI) a otto anni di età.

Sono stati analizzati una vasta gamma di modelli alimentari, valutando: gli aspetti tradizionali, le modalità di preparazione, l’utilizzo di prodotti freschi o preparati, l’allattamento al seno, il consumo di “cibi spazzatura” e di quelli verso i quali potrebbe esistere un’intolleranza.

Poiché nei primi due anni di vita la dieta fornisce le sostanze nutritive necessarie allo sviluppo del sistema nervoso, scopo dello studio è stato quello di analizzare il reale impatto delle abitudini alimentari sul QI dei bambini.

I risultati mostrano che i bambini allattati al seno a sei mesi e, alimentati con una dieta sana e regolare a 15 e 24 mesi (dieta ricca di legumi, frutta e verdura) hanno manifestato, a 8 anni, un QI superiore di due punti rispetto ai bambini cresciuti con una dieta ricca di biscotti, cioccolato, dolci, bibite e patatine fritte nei primi due anni di vita.

Sembrerebbe che un effetto negativo possa essere determinato anche dall’assunzione in età precoce di alimenti già preparati industrialmente e ricchi di conservanti e/o additivi alimentari, ma a questo riguardo i risultati appaiono discordanti.

Le evidenze raccolte sottolineano la necessità di nutrire i bambini con cibi sani fin dai primi anni di vita. Un’alimentazione corretta contribuisce, infatti, al completo sviluppo delle facoltà psichiche. Importante, inoltre, un apporto corretto di acidi grassi della serie omega 3/6, derivati da pesce e verdura, per favorire lo sviluppo generale del bambino e del sistema nervoso centrale.

Anche se le differenze di QI non sono esorbitanti, è stato comunque dimostrato il ruolo cruciale dei modelli alimentari, adottati nel periodo dai 6 ai 24 mesi, per sviluppo cognitivo dei bambini.

Invitiamo a controllare l’alimentazione dei bimbi fin dai primi giorni di vita; fondamentale per lo sviluppo e il nutrimento del neonato è l’alimentazione della madre. Un’alimentazione corretta ed equilibrata, infatti, influenzerà la crescita del bambino, riducendo la possibilità di sviluppare allergie alimentari, dermatite, colite.


Agosto 30, 2012 Newsletter

Negli ultimi anni il crescente interesse per la microflora intestinale ha confermato il ruolo della dieta e dell’integrazione, e ha messo in evidenza gli effetti positivi e negativi prodotti rispettivamente da una condizione eubiotica o disbiotica (disbiosi intestinale).

Recenti studi hanno suggerito importanti relazioni tra l’equilibrio della flora intestinale e alcune malattie del sistema immunitario. Potrebbero, infatti, essere proprio i batteri intestinali a regolare malattie autoimmuni come l’artrite reumatoide. Lo sostiene una ricerca dell’Università dell’Illinois e della Mayo Clinic di Rochester (Minnesota) secondo la quale i batteri intestinali sono fondamentali per la regolazione del sistema immunitario.
 Il lavoro, pubblicato su PloS One, e rilanciato da malattierare.it, è stato realizzato con l’utilizzo di alcune sofisticate tecnologie di sequenziamento genomico, che hanno dimostrato come la microflora intestinale può essere un biomarcatore per la predisposizione all’artrite reumatoide.

L’artrite reumatoide, le cui cause non sono ancora note, colpisce quasi l’1% della popolazione mondiale. Si tratta di una patologia cronica in cui il sistema immunitario attacca i tessuti, infiamma le articolazioni, e talvolta determina complicazioni cardiache che possono anche portare al decesso.
 I ricercatori della Mayo Clinic di Rochester hanno raggiunto importanti progressi nella conoscenza del rapporto tra sistema immunitario e batteri intestinali, e dell’influenza che questi fattori possono avere nelle persone con predisposizioni genetiche alla malattia. Lo studio è stato effettuato su alcuni topi con gene umano HLA-DRB1 0401, forte indicatore della predisposizione all’artrite reumatoide. Grazie a un gruppo di controllo con una diversa variante del gene, gli scienziati hanno confrontato le risposte immunitarie di due gruppi a batteri diversi, valutandone l’effetto sull’artrite reumatoide.

Hanno scoperto, inoltre, che i topi di sesso femminile hanno il triplo della probabilità di sviluppare la malattia.

”Il prossimo passo per noi – hanno dichiarato i ricercatori – è quello di mostrare se i bug presenti nell’intestino possono essere manipolati per cambiare il corso della malattia”.

Utile un controllo della flora intestinale con DISBIOSI test su urine che rivela la concentrazione d’indolo e scatolo intestinale, frutto di un rapporto alterato tra batteri “buoni” e “cattivi”, e un controllo delle feci, la valutazione dei ceppi batterici presenti nell’intestino. Lo studio della flora batterica intestinale attraverso le feci identifica anche la predisposizione a malattie infiammatorie intestinali che possono essere causa di malattie auto immuni sistemiche.

Un’arma terapeutica per la modulazione della flora batterica intestinale è l’idrocolon terapia, che facilità la rimozione dei batteri patogeni, funghi presenti nel lume intestinale, e facilità la riflorazione dei batteri protettivi, attraverso l’introduzione di fermenti specifici e personalizzati.


Luglio 30, 2012 Newsletter

La pitiriasi alba è una comune malattia della pelle, che interessa soprattutto i bambini di età compresa tra i 3 e i 16 anni, con maggiore incidenza nei maschi. Benché sia più evidente negli individui di carnagione scura, colpisce maggiormente gli individui di carnagione chiara.

A oggi, non si conosce la causa della pitiriasi alba. Tali lesioni possono tuttavia presentarsi nel contesto di una dermatite atopica, o di una psoriasi, e tale associazione suggerisce una causa infiammatoria come terreno patogenetico. A sostegno di questa ipotesi vi è, inoltre, il quadro istologico che mostra una diminuzione dei melanociti (le cellule che producono melanina) e dei melanosomi, infiltrazione di cellule infiammatorie linfocitarie a livello del derma e paracheratosi, caratteristica di diversi quadri infiammatori cutanei.

La pitiriasi alba appare come una macchia chiara, bianca, di forma circolare od ovalare, non dolente e non pruriginosa, singola o comunque in numero limitato. A differenza dalla vitiligine, le chiazze non sono mai completamente bianche; la superficie centrale è finemente desquamante, e i margini sfumati.

Le zone di presentazione possono essere ovunque, (soprattutto sulla superficie estensoria delle articolazioni), frequentemente si localizzano a livello della fronte, dell’angolo labbiale, delle guance e degli zigomi. Per il contrasto con la cute circostante, le macchie sono più visibili in estate o comunque sulla cute abbronzata. La diagnosi differenziale si pone con: vitiligine, pitiriasi vescicolare e ipocromie post traumatiche, esiti di precedenti micosi o leucoplachie.

La terapia medica non esiste, essendo un’affezione cutanea autolimitante. A volte blande crema base di cortisone sono utilizzate per brevi periodi per limitare l’estensione della macchia chiara.

La probabile associazione tra pitiriasi alba e intolleranze alimentari, in grado di scatenare una risposta immunoflogistica aspecifica, può essere presa in considerazione se esiste un “terreno” di: predisposizione individuale alle allergie alimentari, pregressa atopia, comparsa di lesioni psoriasiche cutanee.

Una certa attività anticorpale diretta verso i melanociti, creata da infiammazione cronica silente dei linfociti, si può gestire con il controllo degli alimenti riscontrati positivi al test d’intolleranza alimentare ALCAT. Il test verifica il grado di reattività dei granulociti neutrofili verso gli antigeni alimentari, capaci di innescare il processo di immunoflogosi in presenza di reazioni da intolleranza alimentare eccessiva.


Copyright by IMBIO 2017. All rights reserved.