Articoli

Tutto sul nostro settore


Marzo 4, 2014 Newsletter

La mancanza di tempo e lo stile di vita sempre più frenetico portano spesso alla scelta di prodotti da forno di tipo industriale, che spesso utilizzano,per la levitazione dei loro impasti, composti chimici.

Il LIEVITO CHIMICO è infatti costituito da sostanze che, in determinate condizioni, reagiscono tra di loro o con altri componenti dell’impasto per generare gas (quasi sempre anidride carbonica) che permette, come nel caso della lievitazione da lievito di birra, l’espansione dell’impasto.

I lieviti chimici più diffusi sono: CARBONATO DI SODIO, POTASSIO, AMMONIO E MAGNESIO (E500, E 501, E503, E504), TARTRATO DI SODIO (E335), TARTRATO DI POTASSIO (O CREMOR TARTARO, E336), ACIDO TARTARICO (E 334) e

GLUCONE DELTA LATTTONE (E575). Si tratta di composti chimici presenti anche in natura ma che, nella maggioranza dei casi, vengono prodotti per sintesi chimica.

Queste sostanze, per legge, sono classificate come ADDITIVI e sono tecnicamente definite “AGENTI LIEVITANTI”. La loro caratteristica è quella di generare gas molto più velocemente dei loro “parenti” biologici e quindi di risultare più adatte alla preparazione di dolci industriali.

L’azione chimica di questi agenti, tuttavia, non avviene solo nell’impasto ma continua anche nello stomaco e successivamente nell’intestino, favorendo PROCESSI DI FERMENTAZIONE che creano i fastidiosi effetti di GONFIORE, METEORISMO e AEROFAGIA, dati dalla presenza di CO2, che compaiono puntuali al termine di un’abbuffata.

Dagli ultimi studi compiuti dal POLICLINICO SAN MATTEO di PAVIA utilizzando il test ALCAT –

l’unico esame sulle intolleranze riconosciuto in America dalla FDA (Food and Drug Administration)

  • è stato possibile rilevare come, nel corso del 2013, tutti coloro che presentavano un’intolleranza ai LIEVITI nei mesi di NOVEMBRE e DICEMBRE mostravano un’alta positività al LIEVITO CHIMICO. Tale risultato è facilmente comprensibile se si tiene conto del grande consumo di dolci e prodotti da forno LIEVITATI CHIMICAMENTE che vengono consumati durante le vacanze natalizie. Tale situazione crea le condizioni ottimali per lo sviluppo di CANDIDA abicans che, nel mese di GENNAIO, raggiunge il picco di intolleranza (dati ALCAT dall’Ospedale San Matteo di Pavia, anno 2013). La presenza di questo fungo, oltre a provocare gli sgradevoli e conosciuti effetti, predispone anche all’insorgenza di INTOLLERANZE ALIMENTARI a causa dell’aumentata permeabilità della mucosa intestinale (DISBIOSI).

Per scongiurare tale situazione al ritorno delle vacanze, quindi, cercate di evitare, per quanto possibile, dolci e prodotti da forno lievitati chimicamente ed approfittate delle ferie per cucinare dolci fatti in casa con lievito madre, lasciando i “chimici dei dolci” nei loro asettici barattoli.

Articolo di Davide Iozzi, Biologo nutrizionista, esperto in nutrizione umana, collaboratore dell’Istituto di Medicina Genetica Preventiva (I.M.Ge.P.) di Milano.


Febbraio 7, 2014 Newsletter

Una dieta personalizzata basata sul proprio DNA può far nascere un campione…

Esistono in letteratura moltissimi studi che evidenziano come la performance sportiva, soprattutto a livello agonistico, possa essere alterata da una scorretta alimentazione. Nel mondo sportivo odierno, dove sono i dettagli a fare la differenza, dove i decimi o i centesimi di secondo permettono di trionfare alle Olimpiadi o ai Campionati del Mondo, una sana e corretta alimentazione deve essere considerata come un trampolino di lancio per raggiungere l’obiettivo. I sintomi di un’intolleranza alimentare sono diversi, a volte, non si rendono neppure manifesti, rimangono subdoli generando un accumulo di infiammazione. In molti sportivi problemi di natura muscolare, articolare, stanchezza cronica, difficoltà di recupero post gara sono solo alcuni dei sintomi riconducibili ad un’intolleranza alimentare.

La maggior parte degli atleti che praticano sport professionistico di squadra segue spesso un’alimentazione standard, preimpostata, non personalizzata. Si tratta per lo più di menu’ ricchi di carne, pesce, zuccheri, verdure, pasta. E se il nostro atleta fosse geneticamente predisposto ad essere intollerante al glutine? Se il suo organismo fosse predisposto a non tollerare gli zuccheri?

Esperti nutrizionisti potrebbero storcere il naso evidenziando il fatto che non sempre una predisposizione corrisponde ad una manifestazione della patologia. Vero ma non sono forse questi i dettagli che fanno la differenza? Oggi esiste una nuova scienza, la nutrigenetica che studia i rapporti tra il patrimonio genetico, il DNA e la variabilità interindividuale. Con un semplice brush salivare, che ha il vantaggio di poter essere effettuato a qualsiasi età della vita, una volta sola, possiamo personalizzare l’alimentazione e migliorare le prestazioni fisiche. Seguire una dieta rispettosa delle proprie intolleranze alimentari in base al proprio DNA, significa fornire al proprio organismo la giusta benzina per poter esprimere al meglio le qualità fisiche. Monitorando l’alimentazione sin dalle prime fasi dell’agonismo sportivo, potremmo infatti permettere ad un atleta qualsiasi di diventare l’atleta che lui stesso ha sempre sognato di diventare.

Dr Sacha Sorrentino, Imbio Milano – Biologo Nutrizionista Num. iscrizione: AA_069116 – sacha.sorrentino@imbio.it


Ottobre 5, 2013 RASSEGNA STAMPA

Per valutare lo stato nutrizionale di un atleta è bene considerare anche le possibili intolleranze alimentari e il dispendio energetico.

Continuiamo e concludiamo la trattazione della tematica “l’assessment nutrizionale nello sport”, iniziata nel numero 34 de La Palestra, prendendo in esame le intolleranze alimentari e il dispendio energetico dell’atleta. Le reazioni di sensibilizzazione e/o intolleranza a componenti di alimenti, muffe e agenti chimici sono difficili da individuare singolarmente ma esse indubbiamente provocano una serie di alterazioni delle componenti cellulari (in particolare linfociti e piastrine) che
possono essere individuate con specifici Test Ematochimici.

Il test da noi utilizzato è il Test Alcat®, test ematico di valutazione delle intolleranze alimentari.

A cosa serve

Il test ALCAT (ANTIGEN LEUKOCYTE CELLULAR ANTIBODY TEST) permette di dare una soluzione al problema, spesso sottovalutato, delle intolleranze alimentari che si manifestano con una sintomatologia di tipo psico-fisico molto variegata. Cefalea, depressione, scarsa concentrazione, nausea, diarrea, colite epigastralgia, dermatite, eczema, dolore articolare, congiuntivite, edemi e sovrappeso possono spesso esserne le manifestazioni più eclatanti e regredire quasi contemporaneamente all’eliminazione degli alimenti non tollerati.

Le cause delle “intolleranze alimentari” che interessano almeno cinque persone su dieci sono state individuate nello stato di “disbiosi” o alterazione della flora batterica intestinale e nei numerosi “agenti stressanti” che indeboliscono il sistema immunitario intestinale.

Come funziona
Il Test ALCAT si esegue mediante un normale prelievo di sangue che viene poi messo a contatto con cinquanta alimenti di cui si sospetta essere intolleranti. Uno strumento di laboratorio evidenzia una reazione avversa agli alimenti, valutando il numero e le dimensioni di particolari globuli bianchi (granulociti neutrofili).

Quando si verifica una variazione del numero e delle dimensioni dei granulociti neutrofili c’è una reazione avversa a quel determinato alimento. L’esecuzione di questo Test permette a nostro avviso di individualizzare ancora di più il piano nutrizionale dell’atleta andando ad agire soprattutto sui fenomeni infiammatori o su quei sintomi (meteorismo intestinale, cefalea, gastrite, alitosi, sensazioni di gonfiore, dolori muscolari aspecifici) che possono non permettere all’atleta di svolgere al meglio la preparazione all’evento agonistico oppure aumentare una infiammazione Low-Grade negativa anche per la predisposizione all’infortunio, soprattutto di natura muscolare. L’interpretazione del Test non deve essere a nostro avviso troppo rigida e schematica né portare a diete di esclusione ma a diete di rotazione che prevedranno una limitazione dell’assunzione degli alimenti verso cui l’atleta risulta intollerante nel corso della settimana. Durante i ritiri pre partita e nel post partita l’atleta seguirà invece l’alimentazione del team senza particolari limitazioni.

La valutazione del dispendio energetico
La valutazione del dispendio energetico nel calciatore può essere fatta sia con misurazioni di base come la calorimetria indiretta sia a riposo che sotto sforzo che con Holter metabolici che, applicati all’atleta durante lo sforzo fisico, possono dare una valutazione anche settimanale del dispendio di energia . Questi dati devono comunque essere sempre valutati con molta elasticità poiché chiunque si occupi di nutrizione sa quanto è difficile valutare l’effettivo dispendio energetico di un individuo sia a riposo che sotto sforzo.

La composizione corporea
Uno dei metodi da utilizzare assolutamente per il monitoraggio dello stato di benessere dell’atleta è la misurazione della composizione corporea, utilizzabile, tra l’altro, come specchio fedele di un corretto stato nutrizionale sia per quanto riguarda la Massa Grassa (FM) e la Massa Grasso_Priva (FFM), lo stato di idratazione, e gli indici metabolici muscolari (BCM). Risulta intuitivo quanto sia (FFM), lo stato di idratazione, e gli indici metabolici muscolari (BCM). Risulta intuitivo quanto sia importante avere la possibilità di misurare la massa grassa e quella magra per poter definire esattamente lo stato di forma di un atleta, per avere, inoltre, la capacità di intervenire in modo mirato allo scopo, eventualmente, di aumentare la massa magra e diminuire la massa grassa, attualmente le metodiche più utilizzate sono la Bioimpedenziometria Corporea (BIA) e la DEXA.

La BIA sfrutta il diverso comportamento, misurabile, del comparto extracellulare e di quello intracellulare al passaggio di una corrente elettrica alternata. Questi valori, espressi come impedenza, reattanza ed angolo di fase, entrano a far parte di diverse formule matematiche in grado di determinare il valore dell’acqua totale corporea (TBW) scomposta nelle due forme di acqua extracellulare (ECW) ed intracellulare (ICW), inoltre si può calcolare la fondamentale (in particolare per un atleta) quantità di “massa cellulare attiva” (BCM). La BIA vettoriale (o BIVA, da “Bioelectrical Impedance Vector Analysis”) è una metodologia che consente di valutare la composizione corporea dell’atleta dalla misura diretta del vettore impedenza e non dipende né da equazioni né da modelli matematici. Il metodo opera indipendentemente dalla conoscenza del peso corporeo ed è influenzato soltanto dall’errore di misura dell’impedenza e dalla variabilità biologica dei soggetti. La BIVA consente un approccio basato sull’analisi vettoriale delle misure di resistenza e di reattanza fornite dal sensore e divise per l’altezza in metri del soggetto esaminato, in assenza di vincoli a modelli compartimentali o assunzioni sull’idratazione. L’analisi vettoriale è in grado di individuare variazioni dei tessuti molli (massa cellulare) e/o dello stato di idratazione, anche se non offre tutte le informazioni riguardo ai compartimenti di massa grassa e massa magra e non può misurare i volumi dei fluidi corporei. La massa cellulare riflette il tessuto metabolicamente attivo (organi) e quello contrattile (muscolo) e contiene le proteine viscerali e muscolari.

La DXA (Dual Energy X ray Assessement) è una tecnica con cui, utilizzando l’emissione a due livelli energetici di fasci di raggi X a bassissima dose di radiazioni, si possono misurare delle “attenuazioni” proporzionali alla composizione (massa grassa e massa magra) del soggetto ed ottenere, addirittura, la composizione corporea segmentale, cioè dei singoli distretti. La scansione viene eseguita in tempi relativamente brevi, il che, unitamente alla bassissima dose di radiazioni, la rende particolarmente adatta per gli atleti di tutte le età. I valori misurati con metodica DXA per la massa ossea, massa alipidica e massa lipidica sono stati comparati con misure effettuate con altre tecniche.

Conclusioni
Come abbiamo cercato brevemente di illustrare, la valutazione dello stato nutrizionale di un atleta non può prescindere sia dalle valutazioni antropometriche classiche che strumentali, dalla valutazione del dispendio energetico e da una serie di valutazioni ematochimiche ed ormonali.

La valutazione dello stress ossidativo e delle intolleranze alimentari completerà un approccio metodologico che potrà consentire al nutrizionista e allo staff medico di cercare di valutare lo stato nutrizionale dell’atleta ed il suo “livello d’infiammazione” che è indotto dall’attività fisica ad alta intensità e ripetuta nel tempo, permettendo la stesura di un piano nutrizionale e di supplementazione/integrazione, che hanno come primo obiettivo la preservazione dello stato di salute dell’atleta stesso, l’ottimizzazione dei rapporti tra massa grassa e massa magra, il mantenimento di un corretto stato d’idratazione e il controllo dello stato infiammatorio; la conseguenza di questo approccio è il mettere l’atleta nelle migliori condizioni per esprimere le proprie qualità psico-fisiche nella performance, di garantire un buon recupero muscolare dopo lo sforzo, di controllare i livelli di stress e di mantenere, durante l’attività, una buona lucidità psicofisica.

Fabrizio Angelini

scarichi il pdf (37 kb)

Fonte: La Palestra.net – 31 luglio 2011


Modulation of the anticancer immunity by natural agents: inhibition of T regulatory lymphocyte generation by arabinoxylan in patients with locally limited or metastatic solid tumors

lissoniResearch Article (download PDF version)

Paolo Lissoni1,*, Giusy Messina1, Fernando Brivio2, Luca Fumagalli2, Luigi Vigoré3, Franco Rovelli3, Luisa Maruelli4, Mauro Miceli4, Paolo Marchiori4, Giorgio Porro1, Michael Held5, Giuseppe di Fede6, Toshi Uchiyamada7

1 Division of Radiation Oncology, San Gerardo Hospital, Milan, Italy
2 Division of Surgery, San Gerardo Hospital, Milan, Italy
3 Laboratory of Immunomicrobiology, San Gerardo Hospital, Milan, Italy
4 Natur-Spiritual, Milan, Italy
5 Biological Medicine Center, Rome, Italy
6 Institute of Biological Medicine, Milan, Italy
7 Daiwa Pharmaceuticals, Tokyo, Japan

dr. Paolo Lissoni

*Correspondence: Dr. Paolo Lissoni, Divisione di Radioterapia Oncologica, Ospedale S.Gerardo, 20052 Monza, Milano, Italy; Fax: +390392332284, e-mail: p.lissoni@hsgerardo.org
Key words: Anticancer immunity, arabinoxylan, immunostimulation, T regulatory lymphocytes
Abbreviations: interleukin 10, (IL-10); interleukin 6, (IL-6); interleukin-2, (IL-2); interleukn 12, (IL-12); NK cells, (CD16+CD56+); T cytotoxic lymphocytes, (CD8+); T helper lymphocytes, (TH), (CD4+); T lymphocites, (CD3+); Transforming growth factor beta, (TGF-β) T-regulatory lymphocytes, (T-reg), (CD4+CD25+)

Received: 30 September 2008; Revised: 1 November 2008
Accepted: 17 November 2008; electronically published: December 2008

Summary

In the last years, several immunomodulating antitumor agents have demonstrated in the nature, particularly from Aloe plant and rice bran. However, the major problem concerning the natural antitumor agents is to define their immune mechanisms of action in relation to the more recent advances in tumor immunobiology. At present, the main cause responsible for the lack of an effective antitumor response in advanced cancer patients is belived to be represented by the generation of a subtype of T helper lymphocytes (CD4+) with suppressive activity on anticancer immunity, the so-called T regulatory lymphocytes (T reg), which may be clinically identified as CD4+CD25+ cells. On this basis, a study was planned to evaluate the effect of rice bran extract arabinoxylan on T reg cell count and percentage in solid tumor patients in relation to the various lymphocyte subpopulations. The study included 22 evaluable cancer patients, 16 of whom had an untreatable metastatic solid tumor. Arabinoxylan was given orally at a dose of 2000 mg/day for the first month, followed by a dose of 1000 mg/day for the next month. In each patient we evaluated by monoclonal antibodies the absolute number of lymphocytes, T lymphocytes (CD3+), T helper (TH) lymphocytes (CD4+), T cytotoxic lymphocytes (CD8+), NK cells (CD16+CD56+), T reg lymphocytes (CD4+CD25+) and TH/T reg ratio before and after 2 months of therapy. No substantial change occurred on therapy in the mean number of lymphocytes, CD3+, CD8+ and NK cells. On the other hand, the mean number of TH cells increased, whereas that of T reg cell decreased on treatment, even though none of these differences was statistically significant. On the contrary, TH/T reg mean ratio significantly enhanced after arabinoxylan therapy. In addition to its previously demonstrated stimulatory action on NK function, this study shows that arabinoxylan may inhibit the production of T reg cells, which are responsible for cancer-related immunosuppression, with a following improvement in the anticancer immunity. If further studies will confirm these results, arabinoxylan could be successfully associated with chemotherapy to induce not only a cytotoxic destruction of cancer cells, but also an improvement in the immune status.

I. Introduction
The recent advances in the definition of the mechanisms responsible for tumor progression have suggested the possibility to control cancer growth not only trough chemotherapy-induced cancer cell destruction, but also by stimulating the anticancer immunity. In addiction to the exisence of endogenous antitumor molecules, several agents capable of stimulating the anticancer immunity have alsso isolated from plants. However, the immunomodulatory effects of most natural immunomodulating agents need to be better investigated in an attempt to establish their mechanisms of action in relation to the most recent discoveries concerning the physiopathology of the anticancer immunity. At present, Aloe extracts (Lissoni et al, 1998) and arabinoxylan extract from rice bran (Ghoneum and Jewett, 2000) would represent some of the potential natural agents which could be utilized in the complementary therapy of human neoplasms. Today, it is known that the antitumor immune response is the end-result of several interactions involving cytokines and immune cells, provided by stimulatory or suppressive effects on the anticancer immunity (Atzpodien and Kirchner, 1990; Rosenberg, 1992). Therefore, the lack of an effective anticancer immune response in most cancer patients with advanced disease would simply depend on the prevalence of immunosuppressive mechansisms with respect to the immunostimulatory ones (Atzpodien and Kirchner, 1990). The anticancer immunity is mainly activated by T helper-type 1 lymphocytes by releasing IL-2 (Whittington and Faulds, 1993), and by dentritic cells, which act as antigen-presenting cells producing IL-12 (Banks et al, 1995), T cytotoxic lymphocytes and NK-LAK system, which are involved in the induction of the antigen-dependent and antigen-independent cytotoxicity, respectively (Atzpodien and Kirchner, 1990). Therefore, IL-2 and IL-12 would represent the main anticancer cytokines in humans. On the contrary, the suppression of the anticancer immune response is mediated by several cytokines, namely IL-10 (Moore et al, 1993), IL-6 (Matsuda and Hirano, 1990) and TGF-β (Shevach, 2002). Recently, however, it has been demonstrated that the various endogenous suppressive factors would exert their inhibitory immune effect through a common end-mechanism, consisting of the generation of a subtype of T helper lymphocytes (CD4+cells), provided by a fundamental suppressive activity on the anticancer immunity, the so-called T regulatory lymphocyte (T reg) (Dieckmann et al, 2001), which at present seems to constitute the main mechanism responsible for cancer-related immunosuppressive status. T reg cells may be identified by the simultaneous expression of the alpha-chain of IL-2 receptor (CD25) and CD4 antigen (Dieckmann et al, 2001). Then, T reg cells may be clinically recognized as CD4+CD25+ lymphocytes. Therefore, each eventual natural immunomodulating agent would have to be investigated in relation to its possible effect on T reg generation since, at least from a theoretical point of view, each natural agent capable of counteracting T reg activity could positively influence the prognosis of the neoplastic disease by improving the efficacy of the anticancer immune response. Moreover, our previous preliminary studies have suggested that the percentage of T reg cells with respect to the total number of T helper cells, as expressed as CD4/CD4CD25 ratio, may represent an optimal synthetic immune index to investigate the functional status of the anticancer immunity in the single cancer patient, by representing the synthesis of the actions of the great number of immunostimulating and immunosuppressive factors involved in the modulation of the anticancer immunity (Dieckmann et al, 2001). Within the great number of natural agents derived from plants and potentially usefull to be employed in the complementary therapy of cancer, arabinoxylan would seem to represent one of the potential natural agent, because of its efficacy in improving the clinical status of cancer patients (Ghoneum and Jewett, 2000; Ghoneum and Gollapudi, 2005; Markus et al, 2006; Ghoneum et al, 2007). The immunomodulating properties of this nautral substances extracted from plants have been confirmed by experimental studies, but unfortunately most experiments have been limited to the investigations of they effects on non-specific immune parameters for the anticancer immunity, such as NK cell cytotoxicity. In contrast, since reg cells play a fundamental role in suppressing the generation of the anticancer immunty, each potential antitumor immunomodulatory natural substances, would have to be investigated also in relation to their eventual influence on T reg cell system. On the basis of the recent discoveries in tumor immunobiology (Dieckmann et al, 2001; Shevach, 2002), a study was planned to investigate the possible influence of arabinoxylan on both absolute number of T reg cells and their ratio with respect to the total CD4+ T cells in a group of solid tumor patients, affected by locally limited or metastatic disease.

II. Materials and methods
The study included 24 consecutive patients, 18 of whom had a metastatic solid tumor, which did not respond to the conventional anticancer chemotherapies and for whom no other effective standard treatment was available, while the remaining 6 patients had been surgically treated for a locally limited neoplasm. Patients were followed at Biological Medical Institute of Milan and the protocol was approved by the Director of the Institute. Eligibility criteria were, as follows:histologically proven locally limited or metastatic solid tumor, no double tumor, no chronic therapy with corticosteroids because of their immunosuppressive effects and no concomitant treatment with other immunomodulating agents,such as interferons,interleukins and monoclonal antibodies. At the time of the start of arabinoxylan therapy, patients with untreatable metastatic cancer were under treatment with the only supportive care, consisting of anti-inflammatory agents for pain, anti-dopaminergic drugs for nausea and vomiting and with the pineal hormone melatonin for the therapy of the neoplastic cachexia (Banks et al, 1995). Patients were considered as fully evaluable when they had received arabinoxylan therapy for at least 2 consecutive months. Arabinoxylan was given orally at a dose of 1000 mg twice/day for the first month, followed by a dose of 1000 mg/day for the next month. Arabinoxylan was supplied by DAIWA Pharmaceutical (Tokyo, Japan). It was derived from rice bran treated enzymatically with an extract of the shiitake mushrooms. It is a polysaccharide containing β-1,4-xylopironase hemicellulose, commercially available and known as Biobran. For the immune investigation, venous blood samples were collected in the morning after an overnight fast before the onset of arabinoxylan therapy and after 2 consecutive months of treatment. In each blood sample, we evaluated the absolute number of total lymphocytes, T lymphocytes (CD3+), T helper (TH) lymphocytes (CD4+), T cytotoxic lymphocytes (CD8+), NK cells (CD16+ CD56+ and T regulatory (T reg) lymphocytes (CD4+ CD25+). The different lymphocyte subsets were measured with a flow cytometric assay by using specific monoclonal antibodies supplied by Becton-Dickinson (Milan, Italy). Moreover, because of the importance not only of their absolute number, but also of their percentage with respect to the other lymphocyte subsets, namely to that of CD4+ cells, CD4/CD4CD25 ratio, corresponding to TH/T reg ratio, was also determined before and after therapy. Normal values (95% confidence limits) of T reg number and TH/T reg ratio observed in our laboratory were below 240/mm3 and above 4.0, respectively. Data were reported as mean +/- SE and statistically analyzed by the Student’s t test, the analysis of variance and the chi-square test, as appropriate.

III. Results
Evaluable patients were 22/24, while the remaining 2 patients, both affected by untreatable disseminated liver metastases due to colorectal cancer, rapidly died for disease progression before concluding the two planned months of arabinoxylan therapy. The clinical characteristics of the evaluable patients are reported in Table 1. Figure 1 illustrates changes in the mean number of total lymphocytes, T lymphocytes, T cytotoxic lymphocytes and NK cells occurring after 2 months of arabinoxylan therapy. No substantial variation was found in the mean number of lymphocytes, T lymphocytes, T cytotoxic lymphocytes and NK cells under arabinoxylan treatment. In contrast, as illustrated in Figure 2, TH and T reg mean numbers increased and decreased, respectively, after arabinoxylan therapy, without, however statistically significant differences with respect to the values seen prior to therapy. On the contrary, a statistically significant increase in TH/T reg mean ratio was achieved after arabinoxylan therapy (p<0.025). The increase in TH/T reg ratio under arabinoxylan therapy was more pronounced in patients with an abnormally low ratio prior to therapy with respect to that occurring in those with normal pre-treatment ratio, however without statistically significant differences ( 2.3 +/- 0.4 vs 1.7 +/- 0.5). In more detail,
090722_linfocitiT_table1
090722_linfocitiT_1

Figure 1. Changes in the number of lymphocytes, Tlymphocytes (CD3), T cytotoxic lymphocytes (CD8) and NK cells (CD16 CD56) after 2 months of arabinoxylan therapy.
090722_linfocitiT_2

Figure 2. Changes in the mean number of T helper (TH) lymphocytes (CD4) and T regulatory lymphocytes (cd4 cd24) and in TH/T reg mean ratio.

before arabinoxylan therapy, an abnormally low TH/T reg ratio was present in 12/22 (55%) evaluable patients. Arabinoxylan treatment induced a normalization of TH/T reg ratio in 5/12 (42%) patients with an abnormally low ratio prior to therapy. The percentage of arabinoxylan-induced TH/T reg normalization obtained in lymphocytopenic patients was not significantly different from that achieved in patients with normal pre-treatment lymphocyte count ( 3/7(43%) vs 2/5(40%) ). No toxicity was observed under arabinoxylan treatment, which was well tolerated in all patients. Asthenia was present in 8/22 (36%) evaluable patients. An evident relief of asthenia, as assessed by a specific patient report, was obtained under arabinoxylan therapy in 5/8 (63%) patients.

IV. Discussion
Previous experimental studies had already demonstrated some immunomodulating properties of arabinoxylan, in particular consisting of stimulation of NK cytotoxic function (Ghoneum, 1998), whereas NK cell number did not seem to be influenced by arabinoxylan administration. However, it has to be remarked that NK cells were belived to be fundamental in the antitumor immunity until some years ago, before the discovery of the essential role played by the antitumor cytokines, such as IL-2 and IL-12 (Whittington and Faulds, 1993) and dendritic cells, because of their function as antigen-presenting cells (Banks et al, 1995). In fact, it has to be considered that the cytotoxic activity of NK cells is effective only against artificial laboratory cancer cell lines, whose biological malignant properties are different from those presented by fresh human tumor cells (Whittington and Faulds, 1993). In addition, NK cells have been proven to be also able to destroy fresh human cancer cells only after the activation of their cytotoxic function by IL-2 (Atzpodien and Kirchner, 1990). From this point of view, arabinoxylan had been already proven to amplify the stimulatory effect of IL-2 on NK-mediated antitumor cytotoxicity (Ghoneum and Jewett, 2000). In contrast, no study has been performed up to now to evaluate the possible influence of arabinoxylan not only on the mechanisms responsible for the generation of an effective anticancer immune response, but also on those involved in the suppression of anticancer immunity. The results of this preliminary study, carried out to evaluate the influence of arabinoxylan on T reg cells, which represent the most important cells involved in the suppression of the antitumor cytotoxic immune response, demonstrates that arabinoxylan may counteract T reg cell generation by reducing their number and percentage with respect to the total amounts of CD4+ cells and circulating lymphocytes. Since NK cell function is inhibited by T reg activation (Shevach, 2002), the previously demonstrated arabinoxylan-induced stimulation of NK cell cytotoxic function might depend at least in part on its capacity of counteracting T reg generation (Dieckmann et al, 2001). Moreover, this study would suggest that the inhibitory action of arabinoxylan on T reg generation is more pronounced in patients with an abnormally high percentage of T reg cells prior to therapy, with a following pre-treatment abnormally low TH/T reg ratio before therapy, whereas its effect was less evident in patients with a pre-treatment value of TH/T reg ratio within the normal range. Therefore, the influence of arabinoxylan on T reg generation would consist of a modulatory action rather than an inhibitory activity. This finding could explain a potential favourable immunomodulatory effect of arabinoxylan also in patients with autoimmune diseases (Ghoneum, 1998), who in contrast to cancer patients would tend to present abnormally low amounts of T reg cells. In any case, the importance of the inhibition of T reg generation in the induction of an effective anticancer immune response has been recently confirmed by the evidence that the block of T reg activity by specific monoclonal antibodies may induce objective tumor regressions in humans (Yang et al, 2007). Obviously, the major problem is the exact identification of he T reg cell population. Even though T reg cells may express other immune markers, namely FOX-p2 cytoplasmatic antigen, most clinicians are in agreement to identify the CD4+CD25+ cells as T reg lymphocytes (12). In any case, further studies, by evaluating other immune markers, will be required to better identify T reg cells population, namely FOX-p3, even though recently some Authors have shown that FOX-p3 expression by T reg cells is associated with a lower suppressive activity (Dieckmann et al, 2001; Shevach, 2002). Moreover, it has to be remarked that several patients included in the present study were concomitantly under palliative therapy with the anti-cachectic pineal hormone melatonin (Brzezinski, 1997), which may also play immunomodulating effects (Maestroni, 1993). Therefore, further randomized studies with arabinoxylan alone versus arabinoxylan plus melatonin will be required to better define the immunomodulating action of arabinoxylan. If further clinical and experimental studies will confirm the inhibitory action of arabinoxylan on T reg cell system, it could be included in cytokine-based immunotherapies to enhance their efficacy by counteracting T reg cell generation.

References
Atzpodien J, Kirchner H (1990) Cancer, cytokines and cytotoxic cells:interleukin-2 in the immunotherapy of human neoplasms. Klin Wochenschr 14, 1-10.
Banks RE, Patel PM, Selby PJ (1995) Interleukin-12:a novel clinical player in cytokine therapy. Br J cancer 71, 655-659.
Brzezinski A (1997) Melatonin in humans. N Engl J Med 336, 185-195.
Dieckmann D, Plottner H, Berchtold S, Berger T, Schuler G (2001) Ex vivo isolation and characterization of CD4+CD25+ T cells with regulatory properties from human blood. J Exp Med 193, 1303-1310.
Ghoneum M (1998) Enhancement of human natural killer cell activity by modified arabinoxylane fro rice bran(MGN-3). Int J Immunother 14, 89-99.
Ghoneum M, Gollapudi S (2005) Synergistic of arabinoxilan rice bran (MGN-3/Biobran in S. Cerevisiae-induced apoptosis of monolayer breast cancer MFC-7 cells. Anticancer Res 25(6B), 4187-96.
Ghoneum M, Brown J, Gollapudi S (2007) Yeast therapy for the treatment of cancer and its enhancement by MGN-3/Biobran, an arabinoxylan rice bran. Cellular Signaling and Apoptosis Research (Ed. Alex R. Demasi) Cap IV: 185-200.
Ghoneum M, Jewett A (2000) Production of tumor necrosis factor-alpha and interferon-gamma from human peripheral blood lymphocytes by MGN-3, a modified arabinoxylan from rice bran, and its synergy with interleukin-2 in vitro. Cancer Detect Prevent 24, 314-324.
Lissoni P, Giani L, Zerbini S, Trabattoni P, Rovelli F (1998) Biotherapy with the pineal immunomodulating hormone melatonin versus melatonin plus Aloe vera in untreatable advanced solid neoplasms. Nat Immun 16, 27-33.
Maestroni JGM (1993) The immunoneuroendocrine role of melatonin. J Pineal Res 14, 1-10.
Markus J, Miller A, Smith M, Orengo I (2006) Metastatic hemangiopericytoma of the skin treated with wide local excision and MGN-3. Dermatol Surg 32, 145-147.
Matsuda T, Hirano T (1990) Interleukin-6 (IL-6). Biotherapy 2, 363-371.
Moore KW, O’Garra A, De Waal-Malefyt R (1993) Interleukin-10. Ann Rev Immunol 11, 165-174.
Rosenberg SA (1992) The immunotherapy and gene therapy of cancer. J Clin Oncol 10, 181-191.
Shevach EM (2002) CD4+CD25+ suppressor T cells:more questions than answers. Nat Rev Immunol 2, 389-400.
Whittington R, Faulds D (1993) Interleukin-2. Drugs 46, 446-514.
Yang JC, Hughes M, Kammula U, Royal R, Sherry RM, Topalian SL, Suri KB, Levy C, Allen T, Mavroukakis, Lowy I, White DE, Rosenberg SA (2007) Ipilimubab (anti-CTLA4 antibody)causes regression of metastatic renal cell cancer associated with enteritis and hypophysitis. J Immunother 30, 825-830.

(download PDF version)


A clinical study of T-regulatory lymphocyte function in cancer patients in relation to tumor histotype, disease extention, lymphocyte subtypes and cortisol secretion

Research Article (download PDF version)

Luigi Vigorè1, Fernando Brivio2, Luca Fumagalli2, Roberto Vezzo1, Giusy Messina6, Franco Rovelli6, Massimo Colciago3, Giovanna D’Amico4, Giuseppe Di Fede5, Paolo Lissoni6

1 Laboratory of Immunomicrobiology, St.Gerardo Hospital, Monza, Milan, Italy
2 Division of Surgery, St.Gerardo Hospital, Monza, Milan, Italy
3 I.N.R.C.A Laboratory of Analyses, Casatenovo, Lecco, Italy
4 Research Center “Fondazione Tettamanti” Clinica Pediatrica Università Milano-Bicocca, Italy
5 Institute of Biological Medicine, Milan, Italy
6 Division of Radiation Oncology, St.Gerardo Hospital, Monza, Milan, Italy

*Correspondence: Dr. Paolo Lissoni, Divisione di Radioterapia Oncologica, Ospedale S.Gerardo, 20052 Monza, Milano, Italy; Fax: +390392332284, E-mail: p.lissoni@hsgerardo.org
Key words: Anticancer immunity, immunosuppression, T regulatory lymphocytes
Abbreviations: cytotoxic T lymphocyte-associated antigen-4, (CTLA-4); glucocorticoid-induced TNF-α receptor, (GITR); myeloidderived suppressor cells, (MDSC); NK cells, (CD16CD56); T cytotoxic lymphocytes, (CD8); T helper lymphocytes, (CD4); Tregulatory lymphocytes, (T-reg)

Received: 24 July 2008; Revised: 11 September 2008
Accepted: 12 September 2008; electronically published: October 2008

Summary

Several clinical investigations showed that the immune status is a prognostic variable in cancer patients, even tough the evaluation of the anticancer immunity is not generally considered in the medical oncology. Several immune parameters, including lymphocyte subsets and cytokine blood concentration, had been proposed to quantify the functional status of the anticancer immunity, but recent discoveries would suggest that the end-result of the various immune interactions is represented by a subtype of CD4 lymphocytes capable of suppressing the antitumor immune reaction, the so called T-regulatory lymphocytes (T-reg). This study was performed to detect T-reg count and percentage in solid tumor patients, in relation to tumor histotype, disease extension, lymphocyte sub-populations and cortisol circadian secretion. The study included 114 consecutive cancer patients affected by the most frequent tumor histotypes, 69 of whom showed a metastatic disease. In each patient we evaluated T-reg cells, identified as CD4+CD25+, in relation to T helper (CD4), T cytotoxic (CD8) and NK (CD16CD56) cells. Abnormally high values of T-reg cells were seen in 52/114 (46%) patients, and the percentage of high values of T-reg was significantly higher in metastatic patients than in non-metastatic ones. In contrast, no significant difference was seen in relation to tumor histotype. Patients with increased T-reg count had a significantly lower NK cell number. Finally no significant difference in T-reg number was seen between patients with altered or normal rithm of cortisol. The study confirmed that, irrespectively of tumor histotype the metastatic disease is associated with a progressive and increased T-reg generation, with a following suppression of anticancer immunity.

I. Introduction
At present, there is no doubt about the existence of a sub-type of T lymphocytes, the so-called T regulatory lymphocytes (T-reg), capable of suppressing the cellular immune responses,including the anticancer immunity (Thomton and Shevach, 2000; Shevach, 2002; von Herrath and Harrison, 2003; Schwartz, 2005; von Boehmer, 2005; Ziegler, 2006; Zou, 2006). However, the exact definition
of T-reg cells in terms of cell surface marker expression still remains controversial, particularly from a clinical point of view. All authors are in agreement to consider Treg lymphocytes as CD4+CD25+ cells, but at present it is still unknown whether the expression of CD4 and CD25 antigens may be sufficient to identify T-reg cells (Thomton and Shevach, 2000; Shevach, 2002; von Herrath and Harrison, 2003; Schwartz, 2005; von Boehmer, 2005; Ziegler, 2006; Zou, 2006), since several authors retain that the intracytoplasmatic expression of the FOX p3 protein is essential for the differentiation into T-reg cells (Ziegler, 2006; Zou, 2006).Recently, however, some preliminary observations would suggest that the cytoplasmatic expression of FOX p3 by CD4+CD25+ cells may be associated at least in some experimental conditions with a diminished, rather than with an enhanced immunosuppressive activity of T-reg cells (Siddiqui et al, 2007). In contrast, all authors agree that the expression of CD152 antigen, also called cytotoxic T lymphocyteassociated antigen-4 (CTLA-4) (Vasu et al, 2004), is fundamental for the immunosuppressive activity of T-reg cells (Takahashi et al, 2000), since the block of its expression by using anti-CTLA-4 monoclonal antibodies may abolish the suppressive activity of T-reg cells, with a following stimulation of the anticancer immunity in cancer patients (Knutson and Disis, 2007) and an enhanced incidence of autoimmune diseases in the healthy subjects (Lan et al, 2005). Therefore, the addition of a third marker, such as CD152 antigen, may allow to define a more homogeneous cell population provided by a regulatory activity with respect to the simple CD4+CD25+ expression (Dieckmann and Plottner, 2001). In fact, the suppressive regulatory action of CD4+CD25+CD152+ has appeared to be clearly higher than that played by the simple CD4+CD25+ T lymphocytes (Leong et al, 2006).This finding is not surprising, since the simple expression of CD25 marker, corresponding to the !-chain of IL-2 receptor, is not an exclusive characteristic of T-reg lymphocytes, but it is a non-specific property of the overall activated T lymphocytes (Thomton and Shevach, 2000; Shevach, 2002; von Herrath and Harrison, 2003; Schwartz, 2005; von Boehmer, 2005; Ziegler, 2006; Zou, 2006). At present, preliminary clinical studies would show that the percent of circulating CD4+CD25+ cells may be about 10% of the all CD4+ lymphocytes, and that of CD4+CD25+CD152+ cells may be about 40% of the total CD4+CD25+ cells, then the expected percent of CD4+CD25+CD152+ in the healthy subjects would be less than 5% of the total circulating CD4+ lymphocytes (Jago et al, 2004). Finally, the expression of glucocorticoidinduced TNF-α receptor (GITR) is also associated with an evident suppressive activity by T-reg lymphocytes (Kanamaru et al, 2004), which in fact are stimulated by
cortisol (Sthephens et al, 2004), that in contrast may inhibit the activity of the most other T lymphocytes, namely that of T helper lymphocytes, with a following diminished production of IL-2 (Claman, 1998). As far as the mechanisms responsible for T-reg-induced suppression of the anticancer immunity are concerned, several experimental observations have shown that T-reg cells may suppress the antitumor immune response through the release of immunosuppressive cytokines, namely IL-10 and TGF-β (Dieckmann et al, 2002), even though other authors would suggest that the suppressive activity of Treg cells on CD4+ and CD8+ lymphocyte activation may be relatively independent from the action of cytokines, by mainly requiring cell surface contact (Birebent et al, 2004). IL-2 has been proven to be essential for T-reg generation and some authors consider IL-2 as the main growth factor of T-reg lymphocytes (Antony and Restito, 2005), but more adequate studies have demonstrated that IL-2 may induce both stimulation and inhibition of T-reg generation and activation (Malek and Bayer, 2004). In fact, IL-2 has appeared to induce and promote T-reg differentiation only in the presence of TGF-β (Chen et al, 2003). Therefore, IL-2 would constitute the main human cytokine in influencing the characteristics of the anticancer immunity, since it may be responsible for both activation and suppression of an effective immune response against cancer cell proliferation and dissemination (Wang et al, 2001), namely depending on the whole status of the cytokine network, in particular on the presence or in the absence of adequate concentrations of TGF-β. In the absence of TGF-β, IL-2 stimulates the anticancer immunity, whereas it counteracts the generation of an effective antitumor immunity in the presence of TGF-β. In other words, IL-2 would physiologically control both tolerance and immunity, depending on the presence of TGF-β and other less known factors (Annunziato et al, 2002). In fact, under cancer immunotherapy with IL-2 the percent of T-reg cells has been shown to decrease in responding patients and to enhance in those with disease progression (Cesana et al, 2006). However, the regulation of T-reg functions does not depend only on immune factors, since it is also under a neuroendocrine control (Ji et al, 2004). In particular, cortisol has appeared to stimulate T-reg cell generation (Ji et al, 2004), with a following enhanced release of IL-10, by representing the main mechanism responsible for cortisol-induced immunosuppression. From a clinical oncological point of view, preliminary observations showed an enhanced percent of circulating CD4+CD25+ lymphocytes in cancer patients, namely in those with advanced disease (Sasada et al, 2003). The present study was performed to better establish which is T-reg behaviour in cancer patients in relation to both tumor histotype and disease extension.

II. Materials and methods
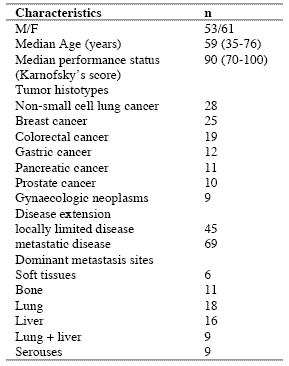
The study included 114 consecutive solid tumor patients with locally limited or metastatic disease, whose clinical characteristics are shown in Table 1. Lung cancer and gastrointestinal tumors were the most frequent neoplasms in our patients. For the immune detections, venous blood samples were collected in the morning after an overnight fast. Operable patients and metastatic patients were investigated before the surgical operation and before the onset of chemotherapy, respectively, in an attempt to exclude the possible influence of the various anticancer therapies on the immune status of patients.

In each sample, we have evaluated total lymphocyte count and the various lymphocyte subpopulations by a flow cytometric assay and monoclonal antibodies, including T helper lymphocytes (CD4), T cytotoxic lymphocytes (CD8), NK cells (CD16CD56), and T regulatory (T-reg) lymphocytes (CD4CD25). Normal values (95% confidence limits) of T-reg observed in our laboratory were below 240/mm3. Moreover, because of its importance in regulating lymphocyte functions and proliferation (Claman, 1998; Sthephens et al, 2004), the circadian rhythm of cortisol was also investigated by collecting blood samples at 8.00 A.M. and at 4.00 P.M., and cortisol serum concentrations were measured in duplicate by using the ECLA method. Data were reported as mean +/- SE, and statistically analyzed by the Student’s t test, the analysis of variance and the chi-square test, as appropriate.

III. Results
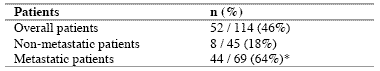
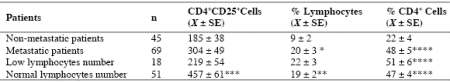
As reported in Table 2, an abnormally high number of T-reg was seen in 52/114 (46%) patients. Moreover, the percentage of cases with elevated number of T-reg observed in metastatic patients was significantly higher with respect to that found in non-metastatic patients (44/69 (64%) vs 8/45(18%), p < 0.01). Table 3 shows the mean number of T-reg and the mean percentages of T-reg with respect to both total lymphocytes and T helper (CD4+) lymphocytes observed in cancer patients in relation to their disease extension. The mean number of T-reg observed in metastatic patients was higher with respect to that found in patients with locally limited disease, without, however statistically significant differences. In contrast, the mean percentages of T-reg with respect to that of both lymphocytes and CD4 cells were significantly higher in metastatic patients than in the non-metastatic ones (p< 0.05 and p< 0.001,respectively). Moreover, within the metastatic group, patients with a normal lymphocyte count greater than 1500/mm3 showed a significantly higher mean number of T-reg with respect to the non-metastatic patients, whereas no difference was seen between nonmetastatic patients and metastatic patients with lymphocytopenia, consisting of lymphocyte count lower than 1500/mm3. In contrast, the mean percentages of T-reg with respect to total lymphocytes and CD4+ cells observed in both groups of metastatic patients with normal or low total lymphocyte count were significantly higher than in non-metastatic patients (lymphocytes: p< 0.025, CD4+ cells: p< 0.001).

Table 1. Clinical characteristics of 114 solid tumor patients
090722_clinicalstud1

Table 2. Percentages of abnormally high values of CD4+CD25+ lymphocytes
090722_clinicalstud2

* P < 0.01 vs non-metastatic patients

Table 3. Mean number of CD4+CD25+ lymphocytes and their mean percentages with respect to total lymphocytes and CD4+ lymphocytes in metastatic and non-metastatic patients
090722_clinicalstud3

* p<0.05 vs non-metastatic patients; ** p<0.025 vs non-metastatic patients; *** p<0.01 vs non-metastatic patients; **** p<0.001 vs nonmetastatic patients

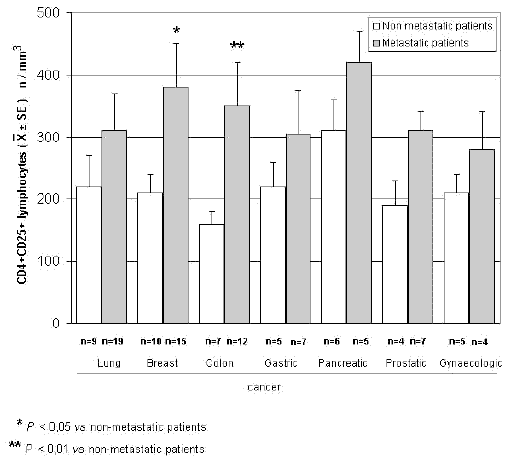
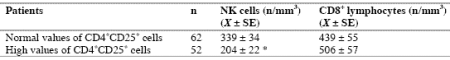
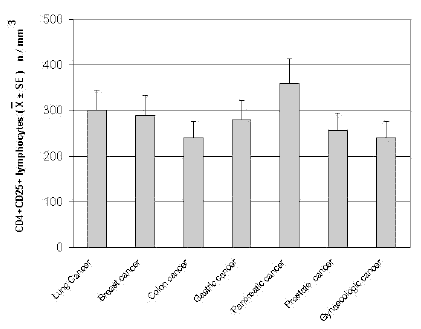
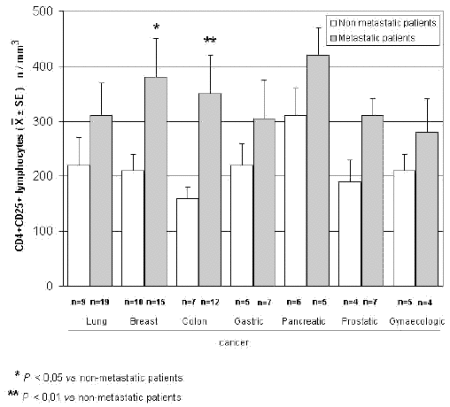
The mean counts of NK and CD8 cells in relation to that of T-reg are reported in Table 4. As shown, no significant difference in the mean number of CD8 lymphocytes was found between patients with normal or abnormally elevated number of T-reg. On the contrary, patients with elevated number of T-reg showed a significantly lower number of NK cells with respect to that found in those with normal T-reg count. Finally, Table 5 shows the circadian rhythm of cortisol in relation to total lymphocytes, CD4+ cells and T-reg mean number. A normal cortisol rhythm, with morning values greater at least than 50% with respect to the values occurring during the afternoon, was found in 85/114 (75%). Total lymphocyte and CD4+ cell mean numbers observed in patients with altered cortisol rhythm were significantly lower than those found in patients with normal cortisol circadianicity (p<0.01), whereas no significant difference was seen in the mean number of T reg. Figure 1 and Figure 2 illustrate T-reg mean numbers in relation to tumor histoptypes in the overall patients and with respect to their disease extension, respectively. No significant difference was seen in relation to tumor histotype. The highest values of T-reg were observed in pancreatic cancer patients, without however significant differences with respect to the overall other histotypes. The metastatic disease was associated with a higher number of T-reg with respect to the non-metastatic group in all tumor histotypes, even though a statistically significant differences occurred for the only breast cancer (p<0.05) and colorectal cancer (p< 0.01).

Table 4. Mean values of NK cells and CD8+ lymphocytes in cancer patients with normal or abnormally high values of CD4+CD25+ lymphocytes
090722_clinicalstud4

* p<0.05 vs normal values of CD4+CD25+ lymphocytes

Table 5. Mean numbers of total lymphocytes, T helper (CD4+) lymphocytes and T regulator lymphocytes (CD4+CD25+) in relation to cortisol circadian secretion in cancer patients
090722_clinicalstud5

* P<0.01 vs patients with altered cortisol rhythm
090722_clinicalstudfig1

Figure 1. CD4+CD25+ lymphocyte mean number in relation to tumor histotype
090722_clinicalstudfig2

Figure 2. CD4+CD25+ lymphocytes in relation to tumor histotype in metastatic and non-metastatic cancer patients

IV. Discussion
According to previous preliminary clinical investigations (Sasada et al, 2003; Cesana et al, 2006), this study confirms in a greater number of cancer patients that the metastatic disease is characterized by the evidence of an abnormally increased percentage of T-reg lymphocytes with respect to both total circulating lymphocytes and CD4+ lymphocytes. This finding does not seem to represent a specific characteristic of some tumor histotypes, then it could constitute a general alteration occurring during the progression of the neoplastic disease, by representing a fundamental immune parameter of cancer-related immunosuppression.

Several immune molecules have appeared to suppress the anticancer immunity, namely IL-6, IL-10, IL-1, TNF-α and TGF-β, but it seems that the common end result of their mechanisms of action may be represented by the stimulation of T-reg generation, with a consequent inhibition of the activation of an effective anticancer immune reaction. On the same way, several immune cells are able to suppress the anticancer immunity, including macrophages, T helper-2 lymphocytes and some myeloidderived suppressor cells, but also in this case they would act in a suppressive way by promoting the generation of Treg.

Then, the detection of T-reg amounts in terms of both absolute number and percentages with respect to total lymphocytes and CD4+ cells could constitute a simple and adequate clinical immune parameter to quantify the whole status of the anticancer immunity in the single cancer patient. Moreover, future clinical studies will be required to establish the possible prognostic significance of changes in T-reg percentage and number in relation to the anticancer efficacy of the various standard antitumor therapies. Moreover, it has to be remarked that T-reg lymphocytes would not represent the only immune cells involved in the suppression of the anticancer immunity. In fact, there is at least another fundamental immunosuppressive system, consisting of the monocytemacrophage cell lineage (Sica and Bronte, 2007). In more detail, it has been observed that the bone marrow may release myeloid precursors provided by suppressive activity on the antitumor immune response and defined as myeloid-derived suppressor cells (MDSC) (Kusmartsev and Gabrilovich, 2005). These cells have appeared to be characterized by the cell surface expression of GR-1, CD11b and CD80 antigens (Anderson et al, 2002; van Ginderachter et al, 2006). The myeloid suppressor cells would promote the generation and activation of T-reg lymphocytes, which at the other side would stimulate MDSC release from the bone marrow and M2 macrophage differentiation (Terabe et al, 2003; Wie et al, 2006).

Moreover, the myeloid suppressive cells would inhibit the anticancer immunity by promoting macrophage differentiation into the M2 sub-type (Ikemoto et al, 2003), which plays a clear inhibitory effect on the anticancer immunity, namely through the release of IL-6 (Ueno et al, 2000), whereas the M1 macrophage sub-type may either stimulate or suppress the antitumor immunity (Mantovani et al, 2004). M1 and M2 macrophage sub-types have appeared to be characterized by a high production of IL-12 or IL-10, respectively (Ueno et al, 2000).

Then, further studies by concomitantly evaluating T reg and MDSC count, will contribute to better define the immune mechanism responsible for the suppression of the anticancer immunity.

References
Anderson CF, Gerber JS, Mosser DM (2002) Modulating macrophage function with IgG immune complexes. J Endotoxin Res 8, 477-81.

Annunziato F, Cosmi L, Liotta F, Lazzeri E, Manetti R, Vanini V, Romagnani P, Maggi E, Romagnani S (2002) Phenotype,localization and mechanism of suppression of CD4+CD25+ human thymocytes. J Exp Med 196, 379-87.

Antony PA, Restito NP (2005) CD4+CD25+ T regulatory cells,immunotherapy of cancer,and interleukin-2. J Immunother 28, 120-8.

Birebent B, Lorho R, Lechartier H, de Guibert S, Alizadeh M,
Vu N, Beauplet A, Robillard N, Semana G (2004) Suppressive properties of human CD4+CD25+regulatory T cells are dependent on CTLA-4 expression. Eur J Immunol 34, 3485-96.

Cesana GC, DeRaffele G, Cohen S, Moroziewicz D, Mitcham J, Stoutenburg J, Cheung K, Hesdorffer C, Kim-Schulze S, Kaufman HL (2006) Characterization of CD4+CD25+ regulatory T cells in patients treated with high-dose interkleukin-2 for metastatic melanoma or renal cell carcinoma. J Clin Oncol 24, 1169-77.

Chen W, Jin W, Hardegen N, Lei KJ, Li L, Marinos N, McGrady G, Wahl SM (2003) Conversion of peripheral CD4+CD25- naïve T cells to CD4+CD25+ regulatory T cells by TGF-β induction of transcription factor Foxp 3. J Exp Med 198, 1875-86.

Claman HN (1998) Corticosteroids and the immune system. Adv Exp Med Biol 245, 203-10.

Dieckmann D, Bruett H, Ploettner H, Lutz MB, Schuler G (2002) Human CD4+CD25+ regulatory contact-dependent T cell induce IL-10 producing,contact-independent type-1-regulatory T cells. J Exp Med 196, 247-53.

Dieckmann D, Plottner H (2001) Ex vivo isolation and characterizationof CD4+CD25+ T cells with regulatory properties from human blood. J Exp Med 193, 1303-10.

Ehrke MJ, Mihich E, Berd D, Mastrangelo MJ (1989) Effects of anticancer drugs on the immune system. Semin Oncol 16, 230-9.

Ghiringhelli F, Larmonier N, Schmitt E, Parcellier A, Cathelin D, Garrido C, Chauffert B, Solary E, Bonnotte B, Martin F (2004) CD4+ CD25+ regulatory T cells suppress tumor immunity but are sensitive to cyclophosphamide which allows Immunotherapy of established tumors to be curative. Eur J Immunol 34, 336-44.

Ikemoto S, Yoshida N, Narita K, Wada S, Kishimoto T, Sugimura K, Nakatani T (2003) Role of tumor-associated macrophages in renal cell carcinoma. Oncol Rep 10, 1843-9.

Jago CB, Yates J, Camara NOS, Lechler RI, Lombardi AG (2004) Differential expression of CTLA-4 among T cell subsets. Clin Exp Immunol 136, 463-71.

Ji HB, Liao G, Faubion WA, Abadía-Molina AC, Cozzo C, Laroux FS, Caton A, Terhorst C (2004) Cutting edge, the natural ligand for glucocorticoid-induced TNF receptorrelated protein abrogates regulatory T cell suppression. J Immunol 172, 5823-7.

Kanamaru F, Youngnak P, Hashiguchi M, Nishioka T, Takahashi T, Sakaguchi S, Ishikawa I, Azuma M (2004) Costimulation via glucocorticoid-induced TNF receptor in both conventional and CD25+ regulatory CD4+ T cells. Immunol 172, 7306-14.

Knutson KL, Disis M, Salazar L (2007) CD4 regulatory T cells in human cancer pathogenesis. Cancer Immunol Immunother 556, 271-85.

Kusmartsev S, Gabrilovich DI (2005) STAT1 signaling regulates tumor-assolciated macrophage-mediate T cell deletion. J Immunol 174, 4880-91.

Lan RY, Ansari AA, Lian ZX, Gershwin ME (2005) Regulatory T cells, development,function,and role in autoimmunity. Autoimmun Rev 4, 351-63.

Leong PP, Mohammad R, Ibrahim N, Ithnin H, Abdullah M, Davis WC, Seow HF (2006) Phenotyping of lymphocytes expressing regulatory and effector markers in infiltrating ductal carcinoma of the breast. Immunol Lett 102, 229-36.

Malek TR, Bayer AL (2004) Tolerance not immunity crucially depends on IL-2. Nat Rev Immunol 4, 665-74.

Mantovani A, Sica A, Sozzani S, Allavena P, Vecchi A, Locati M (2004) The chemokine system in diverse forms of macrophage activation and polarization. Trends Immunol 25, 677-86.

Sasada T, Kimura M, Yoshida Y, Kanai M, Takabayashi A (2003) CD4+CD25+ regulatory T cells in patients with gastrointestinal malignancies, possible involvement of regulatory T cells in disease progression. Cancer 98, 1089-93.

Schwartz RH (2005) Natural regulatory T cells and selftolerance. Nat Immunol 6, 327-30.

Shevach EM (2002) CD4+CD25+ suppressor T cells, more questions than answers. Nat Rev Immunol 2, 389-400.

Sica A, Bronte V (2007) Altered macrophage differentiation and immune dysfunction in tumor development. J Clin Invest 117, 1155-66.

Siddiqui SA, Frigola X, Bonne-Annee S, et al (2007) Tumorinfiltrating Foxp3 CD4+CD25+ T cells predict poor survuival in renal cell carcinoma. Clin Cancer Res 13, 2075-81.

Stephens GL, McHugh RS, Whitters MJ, Young DA, Luxenberg D, Carreno BM, Collins M, Shevach EM (2004) Engagement of glucocorticoid-induced TNFR family-related receptor on effector T cells by its ligand mediates resistance to suppression by CD4+CD25+ T cells. J Immunol 173, 5008-20.

Takahashi T, Tagami T, Yamazaki S, Uede T, Shimizu J, Sakaguchi N, Mak TW, Sakaguchi S (2000) Immunologic and tolerance maintained by CD25+CD4+ regulatory T cells constitutively expressing cytotoxic T lymphocyte-associated antigen. J Exp Med 192, 1285-94.

Terabe M, Matsui S, Park JM, Mamura M, Noben-Trauth N, Donaldson DD, Chen W, Wahl SM, Ledbetter S, Pratt B, Letterio JJ, Paul WE, Berzofsky JA (2003) Transforming growth factor-β production and myeloid cells are an eggector mechanism trhough which CD1d-restricted T cells block cytotoxic T lymphocyte-mediated tumor immunosurveillance, abrogation prevents tumor recurrence. J Exp Med 198, 1741-52.

Thomton AM, Shevach EM (2000) Suppressor effector function of CD4+CD25+ immunoregulatory T cells is antigen nonspecific. J Immunol 164, 183-90.

Ueno T, Toi M, Saji H, Muta M, Bando H, Kuroi K, Koike M, Inadera H, Matsushima K (2000) Significance of macrophage chemo-attractant protein-1 in macrophage recruitment,angiogenesis and survival in human breast cancer. Clin Cancer Res 6, 3282-9.

Van Ginderachter JA, Movahedi K, Hassanzadeh Ghassabeh G, Meerschaut S, Beschin A, Raes G, De Baetselier P (2006) Classical and alternative activation of mononuclear phagocytes, picking the best of both worlds for tumor promotion. Immunobiology 211, 487-501.

Vasu C, Prabhakar BS, Holterman MJ (2004) Targeted CTLA-4 engagement induces CD4+CD25+CTLA-4 high T regulatory cells with target alloantigens specificity. J Immunol 173, 2866-76.

von Boehmer H (2005) Mechanisms of suppression by suppressor T cells. Nat Immunol 6, 338-44.

von Herrath MG, Harrison LC (2003) Regulatory lymphocytes, antigen-induced regulatory T cells in autoimmunity. Nat Rev Immunol 3, 223-32.

Wang XB, Zheng CY, Giscombe R, Lefvert AK (2001) Regulation of surface and intracellularexpression of CTLA-4 on human peripheral T cells. Scand J Immunol 54, 453-8.

Wie S, Kryczeck I, Zou W (2006) Regulatory T-cell compartmentalization and trafficking. Blood 108, 426-31.

Yang R, Cai Z, Zhang Y, Yutzy WH 4th, Roby KF, Roden RB (2006) CD80 in immune suppression by mouse ovarian carcinoma-associated Gr-1+CD11b+ myeloid cells. Cancer Res 66, 6807-15.

Ziegler SF (2006) FOXP3 of mice and men. Annu Rev Immunol 24, 209-26.

Zou W (2006) Regulatory T cells, tumour immunity and immunotherapy. Nat Rev Immunol 6, 295-307.

(download PDF version)



2009: Lissoni P; Fumagalli L; Brivio F; Rovelli F; Messina G; Di Fede G; Colciago M; Brera G
Division of Radiation Oncology, Milan, Italy

Biotherapy with the pineal hormone melatonin plus aloe and myrrh tincture in untreatable metastatic cancer patients as an essence therapy of cancer

Research Article

P. Lissoni1,*, F. Rovelli1, G. Messina2, F. Brivio3, B. Boniardi1, G. Porro1, L.Vigore4, G. Di Fede1, P. Marchiori1, G. Brera5

1 Institute of Biological Medicine, Milan, Italy
2 Psychiatric Division, Policlinico Hospital, Milan
3 Division of Surgery, Bassini Hospital, Cinisello,Milan;
4 Laboratory of Immunomicrobiology,San Gerardo Hospital, Monza, Milan;
5 Ambrosian University, Milan, Italy.

*Correspondence: Dr. Paolo Lissoni, Divisione di Radioterapia Oncologica, Ospedale S. Gerardo, 20052 Monza, Milano, Italia. Fax: +390392332284, e-mail: p.lissoni@hsgerardo.org
Key words: Aloe Vera, Melatonin, Mirrh, and Anticancer Immunity
Abbreviations: Melatonin (MLT), complete response (CR), partial response (PR), stable disease (SD), disease control (DC), progressive disease (PD), T helper lymphocytes (TH, CD4+), T regulatory lymphocytes (T reg, CD4+ CD25+)

Received: 30 July 2009; Revised: 18 October 2009
Accepted: 20 October 2009; electronically published: December 2009

Summary

Background: The recent advances in understanding the immunobiological interactions responsible for cancer progression have allowed us to define the mechanisms of action of some plants, whose antitumor properties were already known by the popular Medicine, in particular Aloe and Myrrha, whose mixture was already therapeutically utilized more than 2000 years ago by the Essence medicine. Moreover, some endogenous natural substances, namely the main hormone produced by the pineal gland melatonin (MLT) may also play anticancer activity. On this basis, a study was performed with a biological regimen consisting of MLT, Aloe and Myrrha in untreatable metastatic cancer patients with life expectancy lower than 1 year. Methods: The study included 35 patients. MLT was given orally at 20 mg/day in the evening and a mixed Aloe and Myrrha tincture was administered at a dose of 5 ml/thrice daily. Results: The clinical response consisted of complete response (CR) in 1, partial response (PR) in 2, stable disease (SD) in 19 patients, whereas the remaining 13 patients had a progressive disease (PD). Thus, a disease control (CR + PR + SD) was achieved in 22/35 (63%)patients. Moreover, a survival longer than 1 year was achieved in 17/35 (49%) patients. Finally, DC was associated with an evident improvement in the immune status, namely consisting of a decrease in the number of T regulatory lymphocytes, which are the main cells responsible for the suppression of the anticancer immunity. Conclusion: This preliminary study shows that a biological anticancer regimen consisting of the pineal hormone MLT in association with Aloe and Myrrha mixture, already known at the times of the Essence medical tradition, may induce a control of the neoplastic disease by stimulating the anticancer immunity, in a relevant percentage metastatic cancer patients, who did not respond to the conventional anticancer treatments and for whom no other standard therapy was available.

References
Davis RH, Parker WL, Sampson RT, Murdoch DP. Isolation of a stimulatory system in an Aloe extract. J Am Pediatr Med Assoc 1991; 81:473-8.

Capasso F, Borrelli F, Capasso R, Di Carlo G, Izzo AA, Pinto L et al. Aloe and its therapeutic use. Phytother Res 1998; 12:124-7.

Vogler BK. Aloe Vera: a systematic review of its clinical effectiveness. B J Gen Pract 1999; 49:823-8.

Claeson P, Zygmunt P, Hogestatt ED. Calcium antagonistic properties of the sesquiterpene T- cadinol. Pharmacol Toxicol 1991; 69:173-7.

Qureshi S, Al-Harbi MM, Ahmed M, Raza M, Giangreco AB, Shah AH. Evaluation of the genotixic, cytotoxic and antitumor properties of Commiphora molmol using normal and Erlich ascites carcinoma cell-bearing Swiss albino mice. Cancer Chemother Pharmacol 1993; 33130-8.

Blazquez C, Casanova ML, Planas A, Del Pulgar TG, Villanueva C, Fernandez-Acenero MJ et al. Inhibition of tumor angiogenesis by cannabinoids. FASEB J 2003; 17:529-31.

Grotenhermen F. Pharmacology of cannabinoids. Neuroendocrinol Lett 2004; 25:14-23.

Aggarwall BB, Kumar A, Bharti AC. Anticancer potential of curcumin. Preclinical and clinical studies. Anticancer Res 2003; 23:363-98.

Lodha R, Bagga A. Tradictional Indian system of Medicine. Ann Acad Med Singapore 2000; 29:37-41.

John’s Gospel 19,38-40.

Iguchi H, Kato KI, Ibayashi H. Age-dependent reduction in serum melatonin concentrations in healthy subjects. J Clin Endocrinol Metab 1982; 55:27-9.

Attanasio A, Borrelli P, Gupta D. Circadian rhythms in serum melatonin from infancy to adolescence. J Clin Endocrinol Metab 1985; 61:388-90.

Jankovic BD. Neuroimmunomodulation. Ann NY Acad Sci 1994; 741:3-38.

Brzezinski A. Melatonin in humans. N Engl J Med 1997; 336:185-95

Bartsch H, Bartsch C. Effects of melatonin on experimental tumors under different photoperiods and times of administration. J neural Transm 1981; 52:269-79

Regelson W, Pierpaoli W. Melatonin: a rediscovered antitumor hormone? Cancer Invest
1987; 5:379-85

Lissoni P. Is there a role for melatonin in supportive care? Supp Care Cancer 2002; 10:110-6.
Sze S, Ng T, Liu W. Antiproliferative effect of pineal indoles on cultured tumor cell lines. J Pineal Res 1993; 14:27-33.

Maestroni GJM. The immunoneuroendocrine role of melatonin. J Pineal Res 1993; 14:1-10.

Lissoni P, Brivio F, Fumagalli L, Messina G,Vigorè L, Parolini D et al. : Neuroimmunomodulation in Medical Oncology: application of Psychoneuroimmunology with subcutaneous low-dose IL-2 plus the pineal hormone melatonin in patients with untreatable metastatic solid tumors. Anticancer Res 2008; 28:1377-82.

Shevach EM. CD4+CD25+ suppressor T cells: more questions than answers. Nat Rev Immunol 2002; 2:389-400.

Rorschach H. Psychodiagnosytics. Ed HA Huber, Bern, Stuttgart, Toronto. Verlag, 1921.

Lissoni P, Messina G, Parolini D, Balestra A, Brivio F, Fumagalli L et al.:A spiritual approach in the treatment of cancer. In Vivo 2008; 22:557-82.


Gennaio 1, 2013 Newsletter

L’alcool è una sostanza di origine naturale proveniente dalla fermentazione e/o distillazione di cereali, frutta o verdura. È conosciuto come la sostanza psicoattiva più antica e più diffusa. Ma se è di origine naturale, come mai può arrivare a creare assuefazione, tossicità ed effetti paragonabili a quelli di una droga ad azione tossica? La risposta sta nella via metabolica utilizzata che fa sì che entri subito nel circolo sanguigno, raggiungendo velocemente il cervello con effetti neurologici immediati. Da qui la dipendenza, il consumo eccessivo fino ad arrivare a squilibri nutritivi e a gravi complicanze per fegato, pancreas, stomaco, sistema nervoso. Alcool e farmaci utilizzano la stessa via metabolica per cui attenzione alle reazioni indesiderate se si assumono medicinali.

Secondo alcuni recenti studi, il “piacere dell’alcool” dipende, insieme con altri fattori, da una predisposizione genetica, così come il “reggere l’alcool” è dovuto al nostro DNA. Il tutto dipende naturalmente dalle dosi assunte, dallo stato di salute e dal metabolismo del soggetto. La dose giornaliera di alcool accettabile corrisponde a 0,6-0,7 g/kg di peso corporeo.

Oggigiorno l’alcolismo è una piaga sociale che colpisce non solo gli adulti, ma anche i più giovani.
L’alcool è la nuova moda degli adolescenti: si comincia con il famoso happy hour per continuare con birra, bevande alcoliche di ogni genere e colore, superalcolici. Non si tratta di “gusto del bere” ma di un mezzo per socializzare fino a raggiungere la dipendenza. Quella diffusa tra gli adolescenti non è di certo la “filosofia” del piacere di gustarsi un buon bicchiere di vino con gli amici! Il vino tra l’altro, anche se alcolico, nelle giuste dosi ha effetti benefici sulla salute. Per la ricchezza nutrizionale che lo distingue, può essere considerato un alimento. Quella del vino è una vera e propria cultura. E’ conosciuto fin dall’antichità per i suoi effetti benefici sull’uomo e ancora oggi diversi studi attestano gli effetti positivi che può avere se consumato con moderazione. Il vino con minori controindicazioni fisiologiche è quello a basso contenuto di tannini, poco alcolico, poco aromatico e non manipolato. Le proprietà benefiche del vino derivano dalla presenza di polifenoli e antociani, sostanze antiossidanti e quindi antitumorali. Inoltre, la presenza di resveratrolo, un polifenolo, gli conferisce la capacità di ridurre il rischio di malattie cardiovascolari. L’acido tartarico invece è un antitumorale specifico per la prostata.

Il vino rosso, rispetto a quello bianco, presenta una maggior concentrazione di polifenoli e quindi una maggior capacità antitumorale. Il vino bianco, essendo un vino meno “strutturato”, e quindi meno forte, necessità dell’aggiunta di conservanti e stabilizzanti, ecco perché è spesso responsabile del cosiddetto “cerchio alla testa”.

La bella notizia è che il vino può essere integrato nei pasti delle diete dimagranti. Al di là del suo contenuto calorico è, infatti, più importante conoscere le caratteristiche degli altri alimenti che compongono un determinato pasto: se ad esempio si tratta di un pasto con un buon apporto di zuccheri, allora sarà bene evitare l’associazione del vino e in particolare sarà il paziente diabetico a dover fare molta attenzione.

Ecco perché consiglio sempre di attenersi al consiglio di uno specialista. Particolare attenzione dovranno fare anche i soggetti con intolleranze alimentari e, parlando di vino, mi riferisco agli intolleranti al nichel ad esempio. Il nichel è un metallo presente nel terreno in grado contaminare frutta, verdura e prodotti da essi derivanti. Le bevande alcoliche possono esserne contaminate anche per il processo di lavorazione che la materia prima subisce. Il nichel è presente nel vino per cui anche in questo caso sarà lo specialista a valutare la situazione nello specifico.

Se invece non avete allergie o intolleranze diagnosticate ma, in seguito ad un paio di bicchieri di vino avvertite sintomi quali difficoltà digestive, reflusso gastrico, eruzioni cutanee, ecc., allora sarà bene effettuare l’ALCAT Test per le intolleranze alimentari (i sintomi da intolleranza possono manifestarsi fino a 48 o anche 72 ore dopo). Nel caso di vino e bevande alcoliche in generale, la causa della vostra intolleranza potrà essere il nichel o uno degli additivi chimici aggiunti durante la lavorazione o l’alimento utilizzato come materia prima. L’ALCAT Test, presente da più di vent’anni nell’ambito dell’alimentazione, e validato da studi diversi condotti presso centri di ricerca, permette di testare alimenti, nichel, additivi chimici (coloranti, conservanti, stabilizzanti) ecc. con un semplice prelievo di sangue. In seguito potrete rivolgervi al vostro medico o nutrizionista di fiducia che vi aiuterà nel risolvere il vostro problema attraverso una terapia nutrizionale e non farmacologica.

Per concludere diciamo che il vino è di certo la bevanda che rende piacevoli i pasti con gli amici, tiene compagnia e ci rende allegri e rilassati ma è bene che non diventi il nostro amico fedele. A tale proposito, dato che può essere per diversi motivi considerato un “medicamento”, ricordiamo sempre che come tutte le medicine va assunto in modo controllato.

a cura della dr.ssa Jessica Barbieri, Biologa Nutrizionista, Consulente IMBIO  Istituto di Medicina Biologica Milano.


Dicembre 1, 2012 Newsletter

La tiroide è una ghiandola endocrina, posta alla base del collo, che insieme ad altre ghiandole e cellule, costituisce il sistema endocrino (ovaie, testicoli, ipofisi, epifisi, ghiandole surrenali, pancreas).

Le ghiandole endocrine producono e riversano nel circolo sanguigno gli ormoni, molecole o “messaggeri chimici” in grado di influenzare e coordinare le diverse attività dell’organismo. Gli ormoni trasmettono segnali tra una parte e l’altra del corpo, e una volta giunti a destinazione agiscono sulla cellula bersaglio, che darà inizio a una particolare attività funzionale.

La tiroide influenza gran parte dell’organismo attraverso la produzione di due ormoni che controllano il metabolismo, ossia la trasformazione del cibo che mangiamo in energia: gli ormoni tri-iodorironina (T3) e gli ormoni Tiroxina (T4).

Per la sintesi di questi ormoni è indispensabile il buon funzionamento dell’ormone ipofisario TSH, un corretto apporto di iodio con la dieta, la presenza dell’aminoacido tirosina, di alcuni enzimi (tireoperossidasi TPO) e del selenio. La produzione di ormoni attivi tiroidei è legata anche alla presenza delle vitamine D, C, E, A.

L’alterazione di questo equilibrio porta a due opposte condizioni patologiche: ipotiroidismo o ipertiroidismo.

L’ipotiroidismo si manifesta in caso di ridotto funzionamento della tiroide che non è in grado di produrre la giusta quantità di ormoni, con conseguente riduzione dell’attività metabolica. Si tratta della patologia tiroidea più diffusa, che colpisce soprattutto le donne (con un rapporto donne e uomini che può essere 5:1).

I sintomi più comuni, che spesso passano inosservati, sono:
stanchezza, freddolosità, letargia, aumento di peso, capelli secchi e sfibrati, pelle secca e ipotonica, caduta dei capelli, stitichezza, mestruazioni più abbondanti, depressione.

L’ipertiroidismo è la condizione opposta: aumento della produzione di ormoni tiroidei, con conseguente aumento della produzione di energia (morbo di Graves-Basedow).
Spesso è di origine auto immune, con produzione di anticorpi rivolti contro il TSH che impediscono il normale funzionamento della ghiandola.
I principali sintomi sono: tremore di tutto il corpo, perdita di peso inspiegabile, sudorazione abbondante, insonnia, agitazione e irrequietezza, tachicardia (battito accelerato del cuore) e ipertensione.

Le patologie della tiroide possono essere diagnosticate in maniera relativamente semplice, vista l’accessibilità clinica della ghiandola stessa, e curate anche grazie a una dieta corretta.

L’alimentazione assume, infatti, un ruolo molto importante in caso di alterazione della tiroide.
In presenza d’ipotiroidismo è necessario ridurre i cibi ad alto contenuto di grassi idrogenati, burro margarine e oil vegetali di origine non nota (diversi dall’olio di oliva), e prevenire la mancanza di minerali fondamentali: ferro, magnesio, selenio Zinco, Iodio; Le vitamine necessarie per un corretto funzionamento sono le seguenti: A, B6, B12, C, D, E.

È consigliato l’uso di sale iodato, mentre sono da evitare le brassicacee (cavolfiore, broccoli e tutta
la famiglia delle crucifere), note per la loro caratteristica di ridurre lo iodio disponibile.

In caso d’ipertiroidismo è bene eliminare tutte le sostanze eccitanti il sistema nervoso: caffeina, cola, bevande energetiche, e un eccesso di proteine animali.

È molto importante, inoltre, per ridurre lo stato infiammatorio generale dell’organismo, valutare la presenza di eventuali intolleranze alimentari, che potrebbero interferire con la funzione tiroidea.
Lo strumento più indicato per la ricerca delle intolleranze alimentari è ALCAT, un test che permette di identificare gli alimenti da evitare, perché potenziali competitori degli ormoni tiroidei, specifici e individuali.

Le indicazioni personalizzate fornite dal medico e dal nutrizionista, possono aiutare a stabilire una corretta alimentazione, mirata a correggere in modo naturale, dove possibile, un iniziale squilibrio metabolico, e le conseguenze del caso.


Novembre 30, 2012 Newsletter

L’allergia al nichel è sempre più diffusa tra gli italiani, non solo tra gli adulti ma anche tra i bambini. La soglia di reattività della nostra pelle, e la capacità di tollerare la presenza di più sostanze contenenti nichel, sembra, infatti, essersi abbassata a causa del contatto con un numero sempre maggiore di allergeni.

Il nichel è un metallo molto diffuso in natura, presente in diversi prodotti: bigiotteria, chiusure lampo, borchie, fibbie delle cinture, bottoni dei jeans, cuoio, creme, coloranti dei tessuti (soprattutto il blu). Anche se non è un ingrediente proprio dei cosmetici, e quindi nessuna etichetta lo riporta, può essere presente in tracce, per motivi d’impurità (strumenti o contenitori che lo rilasciano durante la produzione, bassa purezza degli ingredienti).

La reazione al nichel si manifesta di solito con infiammazioni della pelle di tipo eczematoso nel punto in cui avviene il contatto con il prodotto contenente il metallo, ma può diffondersi in tutto il corpo, con la comparsa di orticaria o bolle pruriginose. Si possono avere anche reazioni infiammatorie delle mucose, con sintomi che possono variare dalla cistite, alla colite, gastrite, esofagite, etc.

Suggerisco di scegliere saponi e detergenti non industriali (semplici ed ecologici), deodoranti ipoallergenici, prestare particolare attenzione alla scelta dei detersivi, consiglio quelli a marchio ecolabel, fare sempre un doppio risciacquo dei panni lavati in lavatrice.

Trattandosi di allergia da accumulo, anche la dieta è importante. Attenzione ai cibi in scatolette di metallo, e a quelli ricchi di nichel: cioccolato, liquirizia, kiwi e altri ancora compresi tra frutta e verdura. È indispensabile un consulto con un nutrizionista medico o biologo, esperto in intolleranze alimentari, in grado di gestire la rotazione degli alimenti contenenti nichel.

Per la diagnosi di allergia al nichel, non sempre agevole, esistono diversi test come i tradizionali prick test, serie sidapa dei metalli. In caso di risultati negativi o poco significativi, un altro test che valuta l’intolleranza al nichel e agli alimenti correlati è il test ALCAT. Si esegue su sangue venoso, quindi tramite prelievo, e analizza alimenti, conservanti e additivi alimentari. In seguito alla diagnosi, sotto consiglio dello specialista, sarà pianificata una dieta ad esclusione, con rotazione e reintroduzione degli alimenti risultati positivi al test.


Novembre 30, 2012 Newsletter

La gravidanza è uno stato particolare durante il quale tutto il metabolismo della donna va incontro a profonde modificazioni. È bene quindi provvedere con un cambiamento nutrizionale in grado di fornire il corretto apporto calorico e tutti i nutrienti necessari alla mamma e alla crescita del bambino.

Durante le visite di routine, peso e bilancia sembrano essere il fulcro cruciale per gran parte di medici e ginecologi. In realtà, accanto al capitolo del controllo del peso, si apre quello sul corretto apporto di macro e micronutrienti e quello riguardante la prevenzione di sindromi allergiche e intolleranze. Per il benessere di mamma e bambino è importante quanto la donna mangia, ma è fondamentale che cosa mangia. La gestazione deve essere un momento di “educazione alimentare” e non di “restrizione”.

Data la posta in gioco, la gravidanza può essere per la donna un’ottima occasione per acquisire nuove conoscenze in ambito nutrizionale come il corretto frazionamento dei pasti durante la giornata, il corretto apporto di tutti i macronutrienti (carboidrati, proteine, fibre, lipidi) e micronutrienti (sali minerali, vitamine) e la prevenzione di allergie e intolleranze.

L’aumento ponderale in gravidanza è strettamente correlato al peso pre-gravidico e al BMI (Boby Mass Index o Indice di Massa Corporea): un BMI corretto e nella norma lascia di solito ben sperare in un aumento di peso corretto rispetto a un BMI da sottopeso o sovrappeso. Nel primo trimestre, è previsto un aumento di peso di circa 2 kg, dal secondo trimestre il controllo deve essere più oculato e non deve essere superiore ai 500g settimanali onde evitare sofferenza fetale.

In generale evitare gli alcolici e limitare i “nervini” (caffè, tè, cacao) che stimolano la contrazione muscolare e quindi anche quella uterina.

E’ bene frazionare i pasti rispettando lo spuntino di metà mattina e metà pomeriggio così da evitare pasti abbondanti che possono aggravare sintomi quali gonfiore, nausea, vomito. Sempre per gli stessi motivi è consigliato evitare cibi “pesanti” quali fritti, piatti troppo conditi, grassi animali (lardo e pancetta), dolci a base di panna e burro. Nei casi di nausea e vomito evitare piatti in brodo, preferire una colazione salata a quella dolce, prediligere le verdure cotte e condimenti a base di limone (ricordiamo che la presenza di vitamina C favorisce l’assorbimento del ferro presente negli alimenti).

È consigliata la massima igiene alimentare e un’abbondante idratazione (2L di acqua al giorno).

Tenere presente l’aumento del fabbisogno nutrizionale e in particolare di vitamine, calcio, potassio, ferro, fosforo e acido folico; da qui l’importanza di un’alimentazione completa. Meglio sopperire a tale fabbisogno da fonti naturali (gli alimenti) prima che dagli integratori (per quanto riguarda l’acido folico, di cui gli alimenti sono poco ricchi, è bene assumere un integratore secondo indicazione medica). Si consiglia di accompagnare i pasti principali con una buona porzione di verdura (meglio se di stagione) e di assumere due porzioni di frutta al giorno. Frutta, verdura e legumi sono ricchi in micronutrienti. Prediligere, inoltre, i cibi integrali (il pane integrale ad esempio contiene sette volte più ferro di quello bianco).

Veniamo ora all’importanza di un’alimentazione sì equilibrata ma allo stesso modo “preventiva”, come già accennato, nei confronti di allergie e intolleranze alimentari. Ad esempio, nei casi di donne particolarmente allergiche, alcuni studi riportano una minore incidenza di forme allergiche ereditarie se, durante la gravidanza, la donna ha seguito un controllo nutrizionale atto a ridurre tutti i nutrienti che potrebbero far scaturire il problema già nel neonato. Preferire quindi alimenti “anallergici” quali carni bianche, pesce, riso, latte di capra, ecc. riducendo il consumo di latte vaccino e latticini, uova e alimenti molto allergenici (fragole, pesche, frutta secca, cacao, ecc.).

La nutrizione della donna gravida deve essere sì “libera” e a suo gusto secondo le cosiddette “voglie”, ma è comunque giusto attenersi a un profilo nutrizionale molto vario così da evitare, o accentuare, intolleranze alimentari nella mamma e quindi “accumuli” nel nascituro.

Se sospettate di essere intolleranti o se semplicemente volete assicurarvi di seguire un’alimentazione corretta anche per il vostro bambino, una buona idea potrebbe essere quella di eseguire il test ALCAT per le intolleranze alimentari. In seguito, un esperto potrà indicarvi il tipo di alimentazione più idonea per voi, così da evitare spiacevoli sintomi in un momento tanto atteso! L’ALCAT Test, diffuso da più di vent’anni e validato da numerosi studi condotti presso centri di ricerca (Fondazione IRCCS Policlinico San Matteo di Pavia, Laboratorio di Immuno-Allergologia, pubblicazioni sulla rivista ufficiale dell’European Academy of Allergology and Clinical Immunology), permette di seguire una terapia non farmacologica ma nutrizionale. Dopo una prima fase di eliminazione dei cibi risultati positivi al test, si procederà con la reintroduzione graduale e controllata di tutti gli alimenti.

In conclusione, oltre che per il rischio di aumento ponderale, il controllo dell’alimentazione della madre in gravidanza è importante per lo sviluppo del feto e per la prevenzione di allergie, intolleranze alimentari, dermatiti atopiche, bronchioliti, coliti, ecc., sintomi che possono presentarsi già dalle prime settimane di vita del bambino.

a cura della dr.ssa Jessica Barbieri, Biologa Nutrizionista, Consulente IMBIO – Istituto di Medicina Biologica Milano.


Copyright by IMBIO 2017. All rights reserved.